


10 September 2026: Articles 
Retroperitoneal Ectopic Bronchogenic Cyst Mimicking an Adrenal Mass: A Case Report and Literature Review
Challenging differential diagnosis, Educational Purpose (only if useful for a systematic review or synthesis), Rare coexistence of disease or pathology
Jie Luo ABDEF 1, Ruixiang Qin ABCG 1*DOI: 10.12659/AJCR.953436
Am J Case Rep 2026; 27:e953436


Abstract
BACKGROUND: Bronchogenic cysts (BCs) are rare congenital anomalies that are extremely uncommon in the retroperitoneum; in this uncommon anatomical location, they are frequently misdiagnosed radiologically as solid adrenal or pancreatic tumors. This report aims to enhance clinical awareness and diagnostic vigilance regarding ectopic retroperitoneal bronchogenic cysts (ERBCs) that closely mimic other common endocrine or urological entities.
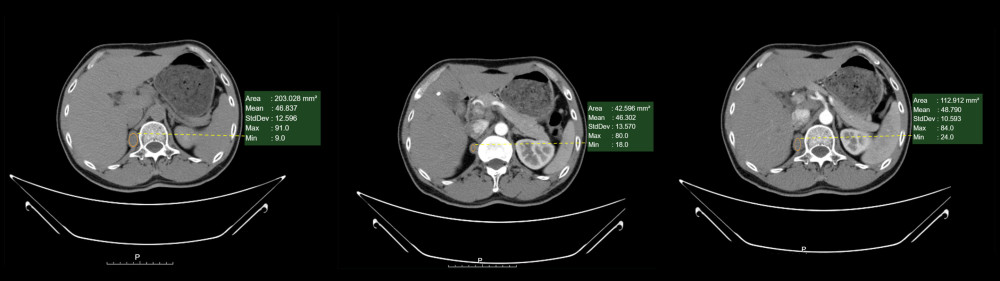
CASE REPORT: We report a case of a middle-aged man presenting with recurrent right flank pain. Abdominal computed tomography (CT) demonstrated multiple right renal calculi with mild hydronephrosis and a well-defined, homogeneous nodular lesion in the right adrenal region. Notably, the lesion exhibited a high unenhanced density (mean 48.79 HU), mimicking a solid adrenal neoplasm. Following comprehensive hormonal and biochemical evaluations, a multidisciplinary team determined that a retroperitoneal tumor could not be ruled out. The patient subsequently underwent laparoscopic resection of the retroperitoneal mass combined with right ureteral stent placement. Intraoperative exploration revealed a morphologically regular adrenal gland and a separate 4×2.5×1.5 cm oval mass located on the psoas major muscle. Histopathological examination confirmed the diagnosis of a benign bronchogenic cyst, characterized by a cyst wall containing prominent cartilaginous components, smooth muscle, and a lining of pseudostratified ciliated columnar epithelium. The patient recovered uneventfully, with complete symptom resolution.
CONCLUSIONS: ERBCs should be included in the differential diagnosis of non-functional lesions in the periadrenal region, especially when atypical high CT attenuation creates diagnostic ambiguity. Minimally invasive laparoscopic excision remains the gold standard for management.
Keywords: Laparoscopy, Diagnosis, Differential, Cysts, Retroperitoneal Neoplasms
Introduction
Bronchogenic cysts (BCs) are rare congenital benign lesions originating from abnormal budding of the primitive foregut [1]. More than 80% occur within the lungs and posterior mediastinum; however, ectopic types can develop in various sites, with the retroperitoneum being the rarest (0.03%) [2]. First reported by Miller et al in 1953 [3], these lesions are typically asymptomatic and diagnosed histopathologically after excision. The objective of this report is to delineate the diagnostic challenges posed by an ERBC mimicking an adrenal tumor in a patient with concurrent renal calculi, thereby providing practical insights into managing overlapping retroperitoneal pathologies.
Case Report
In July 2025, a middle-aged man presented to a local hospital with recurrent right flank pain. Color Doppler ultrasound of the urinary system revealed separation of the right renal collecting system and right renal calculi. The symptoms were temporarily relieved following the administration of analgesics and stone-expulsion therapy. In December 2025, he had a spontaneous recurrence of right flank pain without obvious provocation. The pain was described as a persistent dull ache radiating toward the lower abdomen and perineum. He subsequently sought further evaluation and treatment at the Liangshan Yi Autonomous Prefecture Hospital of Integrated Traditional Chinese and Western Medicine. Upon admission, computed tomography (CT) was performed and demonstrated: (1) multiple right renal calculi associated with mild hydronephrosis; (2) a well-defined, homogeneous, non-enhancing low-attenuation nodular lesion in the right adrenal region measuring 3.5 × 2.5 cm, with a CT attenuation value of 46.5 Hounsfield units (HU) on unenhanced scans and no significant post-contrast enhancement (48.7 HU), exhibiting no clear internal septations or calcifications, suggesting a potential adenoma; and (3) cholelithiasis (Figure 1). Based on the medical history and clinical presentation, the preliminary diagnosis was right renal calculi with secondary hydronephrosis.
To differentiate whether the lesion was a functional adrenal adenoma, the patient underwent comprehensive hormonal and biochemical evaluations. The results were as follows: adrenocorticotropic hormone (ACTH) at 08: 00, 16: 00, and 24: 00 were 66.4 pg/mL (ref: 7–64), 35.95 pg/mL (ref: 3–32), and 11.15 pg/mL (ref: 0–32), respectively; renin was 17.66 pg/mL (ref: 2.4–32.8); and aldosterone was 101.93 pg/mL (ref: 10–160). Serum potassium and sodium levels were 3.99 mmol/L (ref: 3.5–5.3) and 141.0 mmol/L (ref: 137–147), respectively. The blood pressure on admission was 127/84 mm Hg, and no hypertensive episodes were observed during the hospital stay. The daily urine output remained stable at 1500 to 2500 mL.
Following an extensive multidisciplinary team (MDT) discussion among urologists, endocrinologists, and radiologists, the team weighed the borderline ACTH elevation and the radiological findings. Given that a functional adrenal cortical tumor or a non-functional retroperitoneal neoplasm could not be definitively excluded, and considering the patient’s recurrent, intractable symptoms, the surgical team decided to perform laparoscopic resection of the retroperitoneal mass combined with right ureteral stent placement. The primary objectives were to histopathologically characterize the adrenal region mass and to alleviate the right urinary tract obstruction.
Following routine disinfection and trocar placement, the perirenal fat was dissected to expose the adrenal gland. Intraoperative findings revealed a morphologically regular adrenal gland with no identifiable masses. Exploration along the surface of the psoas major muscle at the level of the upper renal pole revealed an oval mass measuring approximately 4 × 2.5 × 1.5 cm within the adipose layer. The mass was soft in texture, well-encapsulated, and had distinct boundaries. It was meticulously dissected along its surface to ensure the integrity of the capsule and subsequently excised for pathological evaluation. The early postoperative course was uneventful. The urinary catheter and surgical drain were removed on postoperative day 3, and the patient was discharged.
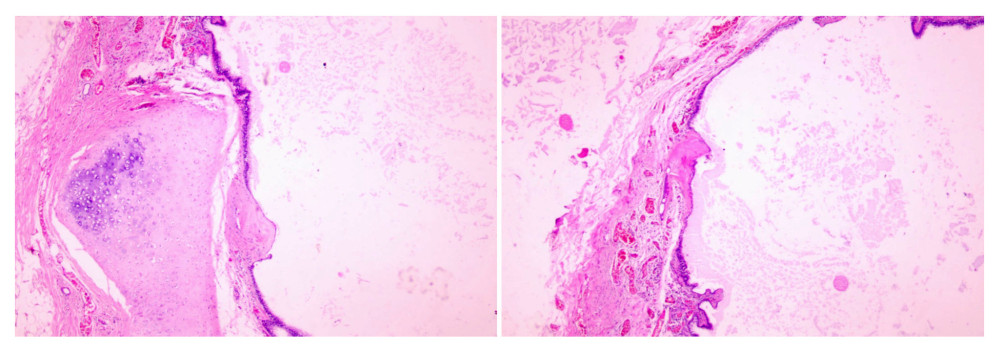
The pathological report described a retroperitoneal cystic lesion measuring 4.5 × 2.5 × 1 cm. Grossly, the cyst was light brown and upon sectioning exhibited a cystic structure containing gelatinous material, with a wall thickness of 0.2 cm. Histopathological examination identified a benign retroperitoneal cyst. The cyst wall contained cartilaginous components and was lined with pseudostratified ciliated columnar epithelium. These findings were consistent with a bronchogenic cyst (Figure 2).
Discussion
Bronchogenic cysts (BCs) are rare clinical entities resulting from abnormal budding of the primitive tracheobronchial tree during early embryogenesis. The tracheobronchial tree originates from the ventral portion of the primitive foregut [4,5]. The fusion of the pleuroperitoneal membranes separates the pericardio-peritoneal canal into 2 distinct cavities, eventually contributing to the formation of the diaphragm. Around the sixth week of gestation, segments of the developing bronchial tree may be sequestered or “pinched off” before completion of the diaphragm. This leads to the ectopic migration of bronchogenic tissue which, as the embryo matures, can further develop into cystic structures in unusual anatomical locations [4].
While these lesions typically manifest within the thoracic cavity [6], ectopic retroperitoneal bronchogenic cysts (ERBCs) are exceedingly rare. A noteworthy feature of our case is the close anatomical proximity of the cyst to the psoas major muscle; this contrasts with the majority of reported ERBCs, which are predominantly located in the vicinity of the left adrenal gland. Retroperitoneal BC was first documented by Miller et al in 1953 [3]. An extensive PubMed search found only 121 cases of retroperitoneal bronchogenic cysts have been recorded in the English-language literature to date. Current data suggests that the incidence is approximately equal between males and females.
The clinical presentations of retroperitoneal bronchogenic cysts (RBCs) are highly variable [7]. Most patients are asymptomatic, with the lesions often discovered as incidental findings during imaging evaluations for unrelated conditions, as demonstrated in the current case. Symptoms, when present, typically arise from the mass effect exerted on adjacent anatomical structures or from complications such as infection, hemorrhage, or perforation. Common manifestations include abdominal or back pain, nausea, and vomiting; in rare instances, hypertension occurs due to compression of the adrenal gland. In our case, although the patient’s symptoms initially subsided after analgesic and lithagogue therapy, the recurrence of pain suggested that treating the renal calculi alone might not have fully addressed the underlying etiology. Clinically, when multiple space-occupying lesions coexist, the potential impact of an ectopic mass should not be overlooked, even if 1 lesion (eg, calculi) appears to explain the symptoms. In our patient, the proximity of the cyst to the adrenal gland and the psoas major muscle suggests that, although the co-existing renal calculi remain the more likely primary cause of the pain, it cannot be entirely ruled out that the cyst, upon reaching a certain size, might have exerted pressure on local nerve plexuses, potentially contributing to or exacerbating the radiating pain.
While the patient in this report underwent successful laparoscopic surgery, the preoperative diagnosis of RBC remains a significant challenge. If a cyst is situated in the periadrenal region, a comprehensive workup—including serum potassium, catecholamines, 24-hour urinary cortisol, and serum adrenocorticotropic hormone (ACTH) levels—is strongly recommended to exclude adrenal pheochromocytoma or adrenocortical tumors. In this instance, the patient’s ACTH levels showed a mild, non-specific elevation, which was of unclear clinical significance and likely related to the patient’s baseline physiological variability or acute discomfort upon admission; given that the blood sample was drawn preoperatively, perioperative stress is an unlikely explanation.
Imaging plays a pivotal role in the diagnostic workup of retroperitoneal bronchogenic cysts (RBCs). On computed tomography (CT), RBCs typically manifest as homogeneous, low-attenuation lesions that exhibit a lack of contrast enhancement, occasionally accompanied by cyst wall calcification. However, CT appearances vary significantly depending on the internal contents of the cyst. High concentrations of mucus or protein can lead to hyperattenuation, which can mimic a solid parenchymal mass.
Magnetic resonance imaging (MRI) is instrumental in identifying the true cystic nature of these lesions [8]. BCs generally exhibit iso- to hyperintense signals on T1-weighted imaging (T1WI) and characteristically high (bright) signal intensity on T2-weighted imaging (T2WI). Despite these typical radiological hallmarks, misdiagnosis remains common [9,10]; consequently, definitive diagnosis necessitates histopathological confirmation. The pathognomonic features of BCs include a well-defined cystic structure lined with pseudostratified ciliated columnar epithelium, interspersed with bronchial glands, smooth muscle, cartilage, and mucoid material.
Surgical resection remains the gold standard for both the diagnosis and treatment of ectopic bronchogenic cysts. The decision to intervene surgically is multifactorial, guided by the presence of symptoms, the growth rate observed over time, and the inherent diagnostic uncertainty regarding the lesion’s benign nature. While the growth kinetics of RBCs are poorly characterized due to their rarity, the primary objectives of resecting enlarging cysts are to alleviate symptoms and prevent potential complications, including infection, hemorrhage, rupture, and, in rare instances, malignant transformation. Furthermore, contemporary evidence underscores that bronchogenic cysts can display dynamic clinical behavior, including progressive enlargement and complicated interactions with adjacent vital retroperitoneal structures over time, which justifies early surgical intervention even for initially asymptomatic lesions.
Malignant transformation in retroperitoneal bronchogenic cysts (RBCs) is exceedingly rare, with an estimated incidence of less than 1% [11]. However, because the radiological features of RBCs are often non-specific and can mimic other benign conditions (eg, cystic teratomas or adrenal masses) surgical resection remains imperative for definitive histopathological diagnosis. In recent years, minimally invasive techniques, including transperitoneal laparoscopic and retroperitoneoscopic approaches, have been widely adopted with excellent clinical outcomes. The retroperitoneoscopic approach is generally considered superior to the transperitoneal route, as it is associated with shorter operative times, reduced postoperative pain, and a shorter duration of hospital stay. In instances where the cyst is densely adherent to surrounding anatomical structures, thorough cauterization of the residual cyst wall is recommended to minimize the risk of recurrence.
Conclusions
When managing retroperitoneal masses in close proximity to the adrenal gland, clinicians must consider ERBC in the differential diagnosis of non-functional lesions, especially when overlapping symptoms like renal colic muddy the clinical picture. Thorough unenhanced and contrast-enhanced CT profiling (focusing on HU stability) helps differentiate them from solid masses. When diagnostic uncertainty persists, early minimally invasive retroperitoneoscopic or laparoscopic resection is highly recommended to establish a definitive histopathological diagnosis, preclude malignant transformation, and permanently relieve potential anatomical compression.
References
1. Pederiva F, Rothenberg SS, Hall N, Congenital lung malformations: Nat Rev Dis Primers, 2023; 9(1); 60
2. Xie W, Huang Z, Huang Z, Retroperitoneal bronchogenic cyst with fluid-fluid level: A case report and literature review: Exp Ther Med, 2023; 25(1); 5
3. Miller RF, Graub M, Pashuck ET, Bronchogenic cysts; Anomalies resulting from maldevelopment of the primitive foregut and midgut: Am J Roentgenol Radium Ther Nucl Med, 1953; 70(5); 771-85
4. Weissferdt A, Non-neoplastic thoracic cysts: A clinicopathologic study of 136 cases: Am J Surg Pathol, 2023; 47(12); 1349-63
5. Matsumoto H, Hasegawa S, Maezawa Y, An atypical presentation of bronchogenic cyst: Klin Onkol, 2024; 37(6); 463-66
6. Senturk TE, Topaloglu O, Spontaneous tracheal fistulization of a progressive bronchogenic cyst: A four-year conservative follow-up case report: Arch Bronconeumol, 2026; 62(2); 139-40
7. Gostomczyk K, Borowczak J, Zdrenka M, Szylberg L, Atypical presentation of bronchogenic cyst in the retroperitoneal space: Cureus, 2024; 16(2); e55029
8. Singh AK, Neyaz Z, Verma R, Diagnostic yield and safety of percutaneous CT-guided biopsy of retroperitoneal lesions and analysis of imaging features: Acta Radiol, 2022; 63(2); 149-58
9. Wen Y, Chen W, Chen J, He X, Retroperitoneal bronchogenic cyst resembling an adrenal tumor: Two case reports and literature review: J Int Med Res, 2020; 48(5); 300060520925673
10. Runge T, Blank A, Schafer SC, A retroperitoneal bronchogenic cyst mimicking a pancreatic or adrenal mass: Case Rep Gastroenterol, 2013; 7(3); 428-32
11. Herrera-Almario GE, Nunez-Rocha RE, Gomez-Samper AF, The use of retroperitoneoscopy in the biopsy of retroperitoneal lesions: How I do it: Am J Surg, 2022; 224(1 Pt B); 443-44
In Press
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954777
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953433
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953495
Case report
Am J Case Rep In Press; DOI: 10.12659/AJCR.953909
Most Viewed Current Articles
07 Dec 2021 : Case report  24,528,339
DOI :10.12659/AJCR.934347
Am J Case Rep 2021; 22:e934347
06 Dec 2021 : Case report  179,580
DOI :10.12659/AJCR.934406
Am J Case Rep 2021; 22:e934406
21 Jun 2024 : Case report
123,371
DOI :10.12659/AJCR.944371
Am J Case Rep 2024; 25:e944371
07 Mar 2024 : Case report
67,776
DOI :10.12659/AJCR.943133
Am J Case Rep 2024; 25:e943133