


12 September 2026: Articles 
Airway Emergency in a Primigravida Associated With Paradoxical Vocal Fold Motion and Placental Abruption Leading to Emergent Cesarean Delivery: A Case Report
Unusual clinical course, Challenging differential diagnosis, Management of emergency care
Emily G. Bliss EF 1*, Bryce M. Marshall EF 1, Gregory L. Rose E 1, Neva P. Lemoine EF 2, James K. Damron EF 2
DOI: 10.12659/AJCR.953653
Am J Case Rep 2026; 27:e953653


Abstract
BACKGROUND: Paradoxical vocal fold motion disorder (PVFM) is a rare condition consisting of episodic upper airway obstruction, resulting in recurrent stridor and respiratory distress. Limited data exists regarding its presentation, implications, and consequences during pregnancy. In this report, we present the case of a 23-year-old primigravida woman with known PVFM and recurrent stridor who developed acute respiratory distress requiring endotracheal intubation, followed by emergency bedside cesarean delivery, during which an incidental placental abruption was identified.
CASE REPORT: A 23-year-old primigravida woman with known history of PVFM underwent bilateral vocal fold botulinum toxin injections. She was re-admitted one week after being discharged with recurrent stridor, which temporarily responded to symptomatic management. However, she subsequently developed acute respiratory distress necessitating intubation. She then required emergency bedside cesarean section in the intensive care unit (ICU) for non-reassuring fetal heart tones, in which a placental abruption was incidentally discovered.
CONCLUSIONS: This case highlights the potential for pregnancy-related anatomic and physiologic airway changes to exacerbate PVFM, creating challenges for emergency airway management in non-operating room settings. It also suggests an association between acute-on-chronic PVFM episodes and placental abruption. We conclude that pregnant patients with PVFM must be monitored closely and considered to be at increased risk for difficult emergency airways and maternal respiratory distress than can lead to placental abruption.
Keywords: Abruptio Placentae, Cesarean Section, Obstetric Labor Complications, Placental Circulation, vocal cord dysfunction, Case Reports
Introduction
Paradoxical vocal fold motion disorder (PVFM), also referred to as vocal cord dysfunction, inducible laryngeal obstruction, and historically termed “hysteric croup”, is a rare but well-described type of functional voice disorder. It commonly presents as sudden onset intermittent stridor and respiratory distress secondary to upper airway obstruction during inhalation [1]. It is often misdiagnosed as refractory asthma, leading to excessive hospitalization, medication use, tracheal intubation, and, in severe cases, tracheostomy [2]. This challenge in determining a clear diagnosis makes the true incidence of PVFM difficult to determine, but the estimated prevalence in the United States is approximately 0.98% [1,3]. PVFM is most commonly diagnosed during infancy (infantile PVFM) or childhood based on clinical history, physical examination, spirometry, oxygen desaturation during episodes, response to treatment, and, most definitively, laryngoscopy for direct visualization of the vocal folds [1,3]. Underlying causes, while not completely understood, includes a hyperactive, dysfunctional response to chronic irritation from acid reflux, allergens, inflammation, edema, or infection [1,2]. PVFM has been shown to respond to botulinum toxin, voice therapy, and treatment of underlying irritants [4]. Despite this, there is a paucity of information regarding PVFM in pregnancy and its impact on maternal-fetal morbidity and mortality. In this report, we present the case of a 23-year-old primigravida woman with known PVFM and recurrent stridor who developed acute respiratory distress requiring endotracheal intubation, followed by emergency bedside cesarean delivery, during which an incidental placental abruption was identified.
Case Report
A 23-year-old primigravida woman presented at 33 weeks 3 days gestation in respiratory distress with audible stridor secondary to paradoxical vocal fold motion disorder. Her medical history included gestational diabetes, gestational hypertension, asthma, ADHD, and depression. Episodes of respiratory distress and stridor began a few years prior to pregnancy, with an unknown etiology, necessitating multiple admissions to the intensive care unit (ICU) for intubation and mechanical ventilation with documented paradoxical vocal fold motion. Before the pregnancy, her symptoms were controlled with regular botulinum toxin injections, but they were discontinued when she became pregnant. Without the injections, and with pregnancy continuing to exacerbate the severity and frequency of her symptoms, she required multiple hospital admissions for attempted management with nebulized racemic epinephrine, nebulized lidocaine, midazolam, and bi-level positive airway pressure (BiPAP) therapy.
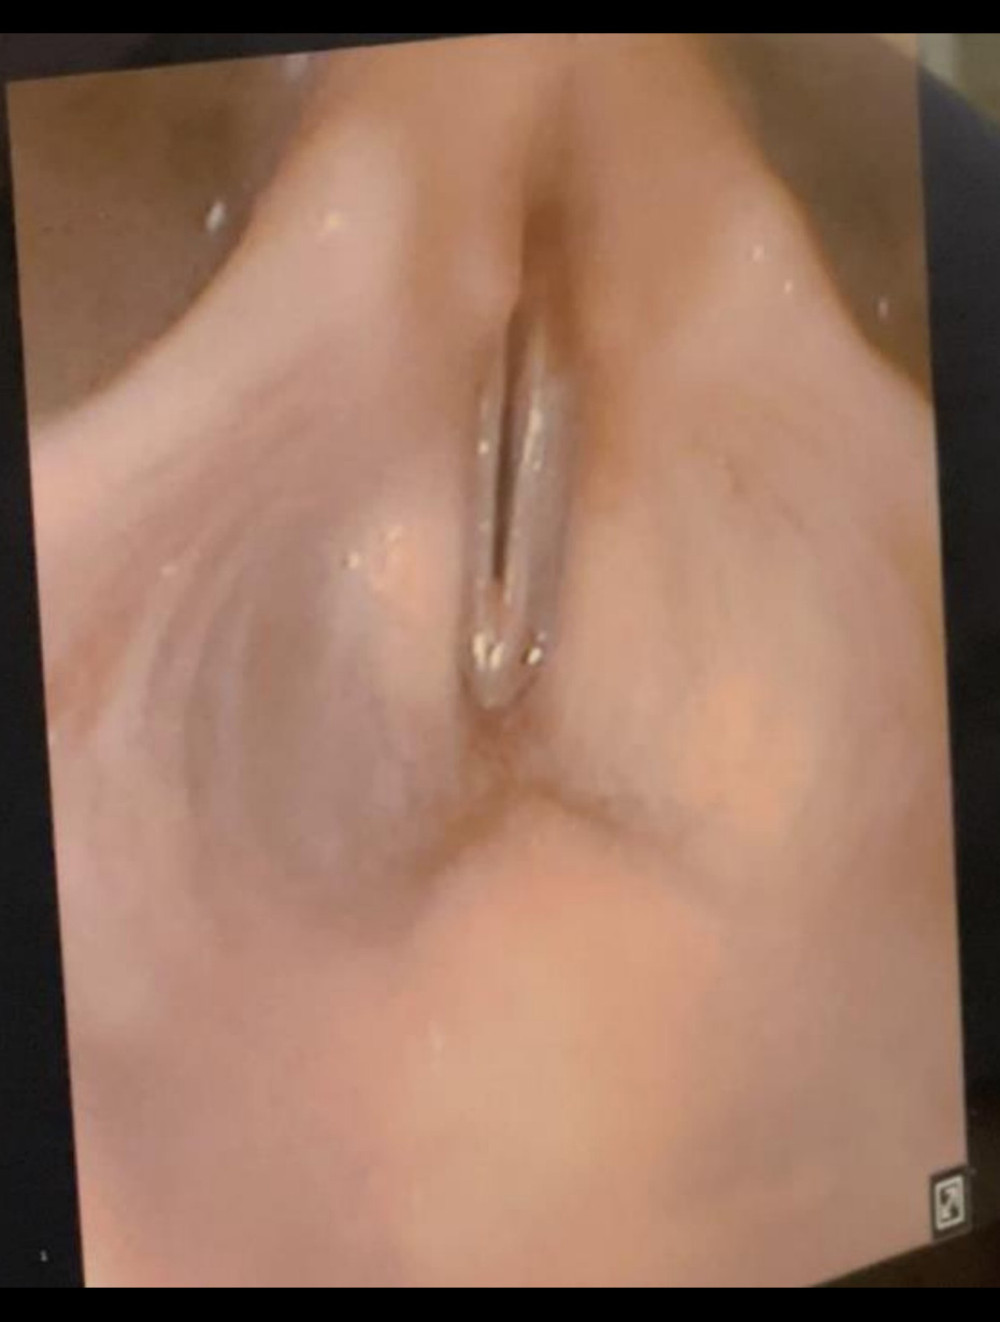
On day 2 of this admission, due to continued episodes that failed to respond to alternative management, she underwent bilateral vocal cord injections with botulinum toxin. During the procedure, multiple episodes of paradoxical movement with adduction on inhalation were observed (Figure 1). She was discharged on hospital day 4 with symptom resolution, but she re-presented the following week for recurrent stridor. She was admitted directly to the ICU on BiPAP therapy with induction of labor scheduled for 36 weeks.
On readmission day 1, she experienced acute-onset respiratory distress with worsening audible stridor. While preparing for intubation, continuous fetal monitoring became difficult to maintain. A bedside ultrasound showed fetal bradycardia at 60 beats per minute, prompting an emergency cesarean section. Due to the patient’s instability and the distance to an available operating room, the decision was made to proceed with the procedure at the bedside in the ICU. General anesthesia was induced, and her airway was secured using video laryngoscopy by the obstetric anesthesiology team due to an anticipated difficult airway. She was placed on the ICU ventilator and general anesthesia was maintained with a propofol infusion. A viable male neonate was delivered; however, bloody amniotic fluid was noted, consistent with the incidental finding of placental abruption. The patient was successfully extubated on postoperative day 1.
Discussion
When present, PVFM should be recognized by anesthesia providers as a potential contributor to difficult intubation, particularly in non-operating room settings, as well as a cause of maternal respiratory distress that can increase the risk of adverse fetal outcomes, including placental abruption. At baseline, anatomic changes throughout pregnancy can result in difficult airways. Physiologic changes associated with increased estrogen levels promote vasodilation within mucosal membranes, resulting in edema of the upper airways and vocal folds [5,6]. Voice changes, including decreased pitch, are commonly reported and thought to be secondary to vocal fold edema [6]. These variables, in addition to the intermittent vocal cord adduction present in PVFM disorder, can lead to increasing difficulty with intubation. We also theorize that these changes further increase the frequency and severity of vocal cord dysfunction in pregnant patients with underlying PVFM, increasing the likelihood of recurrent hypoxic events, similar to asthma or bronchitis, which can lead to adverse neonatal outcomes.
One retrospective cohort study found a correlation between mothers with asthma and complications including preterm birth, hypertensive disorders of pregnancy, and placental abruption [7]. Other well-established risk factors of placental abruption include hypertension, smoking, drug use (including cocaine), and advanced maternal age [8]. However, the association between acute and chronic respiratory conditions and placental abruption is less well-described. Additional studies have found a strong correlation between chronic bronchitis and placental abruption [9]. During episodes of severe PVFM, decreases in maternal oxygenation and reduced placental blood flow can increase the risk of fetal hypoxia and placental abruption, similar to the physiologic changes seen during an acute asthma or bronchitis exacerbation. We theorize that recurrent acute PVFM episodes throughout pregnancy, as seen in this patient, can result in recurrent hypoxic events leading to pathologic maternal-placental vascular changes with acute episodes serving as mechanical triggers for abruption via vasospasm [10,11]. Therefore, patients with PVFM should be considered at an increased risk for placental abruption.
Conclusions
This report describes the case a primigravida woman with an acute-on-chronic episode of PVFM that resulted in maternal respiratory distress necessitating intubation, followed by an emergency bedside cesarean section in the ICU, in which a placental abruption was incidentally noted. Although not well characterized in pregnancy, PVFM can worsen due to pregnancy-related anatomic and physiologic changes, increasing episode frequency and severity, and further complicating maternal airway management. This further provides a unique challenge in non-operating room settings. PVFM results in recurrent hypoxic events similar to acute and chronic respiratory conditions, such as asthma and bronchitis, increasing the risk of placental abruption due to pathologic vascular changes, with acute episodes serving as a mechanical trigger. We conclude that patients with PVFM in pregnancy must be monitored closely and should be considered at increased risk for difficult emergency airways and maternal respiratory distress than can lead to placental abruption.
References
1. Hicks M, Brugman SM, Katial R, Vocal cord dysfunction/paradoxical vocal fold motion: Prim Care, 2008; 35(1); 81-103
2. Ibrahim WH, Gheriani HA, Almohamed AA, Raza T, Paradoxical vocal cord motion disorder: Past, present and future: Postgrad Med J, 2007; 83(977); 164-72
3. Naqvi Y, Gupta V, Functional voice disorders. [Updated 2023 Apr 28]: StatPearls [Internet], 2026, Treasure Island (FL), StatPearls Publishing Available from: https://www.ncbi.nlm.nih.gov/books/NBK563182/
4. Vance D, Heyd C, Pier M, Paradoxical vocal fold movement: A retrospective analysis: J Voice, 2021; 35(6); 927-29
5. Ejikeme C, Nandakumar V, Gotur D, Respiratory physiological changes in pregnancy: Respir Med, 2025; 246; 108245
6. Li X, Xu W, Clinical characteristics of women with low vocal pitch during pregnancy: J Voice, 2021; 35(1); 113-15
7. Liu S, Wen SW, Demissie K, Marcoux S, Kramer MS, Maternal asthma and pregnancy outcomes: A retrospective cohort study: Am J Obstet Gynecol, 2001; 184(2); 90-96
8. Sullivan M, Skelly CL, Rouse C, Placental abruption. [Updated 2025 Dec 13]: StatPearls [Internet], 2025, Treasure Island (FL), StatPearls Publishing Available from: https://www.ncbi.nlm.nih.gov/books/NBK482335/
9. Getahun D, Ananth CV, Peltier MR, Acute and chronic respiratory diseases in pregnancy: Associations with placental abruption: Am J Obstet Gynecol, 2006; 195(4); 1180-84
10. Krikun G, Huang ST, Schatz F, Thrombin activation of endometrial endothelial cells: A possible role in intrauterine growth restriction: Thromb Haemost, 2007; 97(2); 245-53
11. Tikkanen M, Etiology, clinical manifestations, and prediction of placental abruption: Acta Obstet Gynecol Scand, 2010; 89(6); 732-40
In Press
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.952499
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953531
Case report
Am J Case Rep In Press; DOI: 10.12659/AJCR.953461
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954251
Most Viewed Current Articles
07 Dec 2021 : Case report
22,774,712
DOI :10.12659/AJCR.934347
Am J Case Rep 2021; 22:e934347
06 Dec 2021 : Case report  179,275
DOI :10.12659/AJCR.934406
Am J Case Rep 2021; 22:e934406
21 Jun 2024 : Case report
123,110
DOI :10.12659/AJCR.944371
Am J Case Rep 2024; 25:e944371
07 Mar 2024 : Case report
67,547
DOI :10.12659/AJCR.943133
Am J Case Rep 2024; 25:e943133