


19 September 2026: Articles 
Campylobacter jejuni as a Rare Pathogen in CIED Pocket Infections: A Case Report and Literature Review
Challenging differential diagnosis, Rare disease, Educational Purpose (only if useful for a systematic review or synthesis)
Karolina Barańska-Pawełczak ABEF 1*, Bettina Ziaja EF 1, Mariusz Opara BEF 1, Wojciech Jacheć ABDF 2
DOI: 10.12659/AJCR.953738
Am J Case Rep 2026; 27:e953738


Abstract
BACKGROUND: Cardiac implantable electronic device (CIED) infections are usually caused by gram-positive bacteria, whereas gram-negative pathogens are uncommon.
CASE REPORT: We report a case of pacemaker pocket infection caused by Campylobacter jejuni in an immunocompromised patient. The patient underwent uncomplicated dual-chamber pacemaker implantation for sick sinus syndrome. At the first scheduled follow-up, after receiving a diagnosis of primary central nervous system diffuse large B-cell lymphoma and beginning chemotherapy with corticosteroids, swelling and subcutaneous fluid accumulation over the device pocket were observed. There were no local inflammatory signs; the patient had no systemic symptoms or recent history of diarrhea, abdominal pain, nausea, vomiting, or other gastrointestinal symptoms. Inflammatory markers were mildly elevated. Device pocket aspiration yielded straw-colored serous fluid; cultures of pocket fluid and blood grew C. jejuni, prompting a change from empirical amoxicillin-clavulanate to targeted macrolide therapy (intravenous clarithromycin) based on antimicrobial susceptibility testing. Transesophageal echocardiography showed no vegetations on the leads. The entire pacing system (generator and leads) was extracted, and temporary pacing was provided. Inflammatory markers became normalized during continued antibiotic therapy. After clinical stabilization, a new dual-chamber pacemaker was implanted contralaterally. The patient was discharged without signs of persistent infection and remains under regular outpatient follow-up.
CONCLUSIONS: This case emphasizes that subtle pocket changes in immunocompromised patients may indicate CIED infection, even in the absence of systemic symptoms. The absence of gastrointestinal symptoms suggests silent Campylobacter bacteremia with secondary seeding of the device pocket. Early microbiological sampling, pathogen-directed antimicrobial therapy, and complete device removal remain essential for cure.
Keywords: Pacemaker, Artificial, infections, Device Removal, Device Lead Extraction
Introduction
Cardiac implantable electronic device (CIED) infections are clinically important complications of electrotherapy procedures, with a reported incidence generally ranging from approximately 1% to 2% in contemporary studies [1–4]. Infection may result from contamination at the time of implantation or from hematogenous spread involving a distant infectious focus. The risk increases in patients with comorbidities such as diabetes mellitus, renal dysfunction, malignancy, or immunosuppressive therapy; it also increases after repeated device-related procedures [5–7]. Most CIED infections are caused by gram-positive bacteria, particularly
Here, we present a case of atypical pacemaker pocket infection caused by
Case Report
A 74-year-old man was referred for permanent pacemaker implantation due to sick sinus syndrome presenting with pre-Morgagni-Adams-Stokes symptoms, including dizziness and presyncopal episodes. Several weeks before the initial admission, he had been diagnosed with a frontal lobe brain tumor with corpus callosum infiltration; he had been undergoing continuous neurological evaluation. His medical history was notable for hypertension treated with losartan 50 mg and furosemide 40 mg daily, as well as type 2 diabetes mellitus treated with metformin and insulin therapy, including rapid-acting insulin administered 3 times daily (20–24 units daily in total). Electrocardiography revealed predominant sinus bradycardia with first-degree atrioventricular block (PQ interval, 220 ms). Transthoracic echocardiography showed no clinically significant abnormalities. A dual-chamber pacemaker was implanted without procedural complications. Lead position was confirmed radiographically. The following day, the patient was discharged home with recommendations for outpatient device follow-up and continuation of the oncological evaluation.
Nine days after pacemaker implantation, a stereotactic biopsy was performed; histopathological examination established the diagnosis of primary central nervous system diffuse large B-cell lymphoma 3 days later. The International Extranodal Lymphoma Study Group prognostic score was 3. Chemotherapy with the R-COP regimen—consisting of rituximab, cyclophosphamide, vincristine, and prednisone—was initiated approximately 7 weeks after the initial admission. Additionally, the patient received chronic dexamethasone therapy (4 mg twice daily) between chemotherapy cycles.
During the first scheduled device follow-up, approximately 3 months after implantation and approximately 6 weeks after chemotherapy initiation, swelling of the pacemaker pocket with visible subcutaneous fluid accumulation and increased contour—but without signs of local inflammation—was observed. The patient had no symptoms of a systemic inflammatory response. Device electrical parameters were within normal limits (ventricular lead threshold, 0.375 V; impedance, 470 Ω; atrial lead threshold, 0.325 V; impedance, 614 Ω).
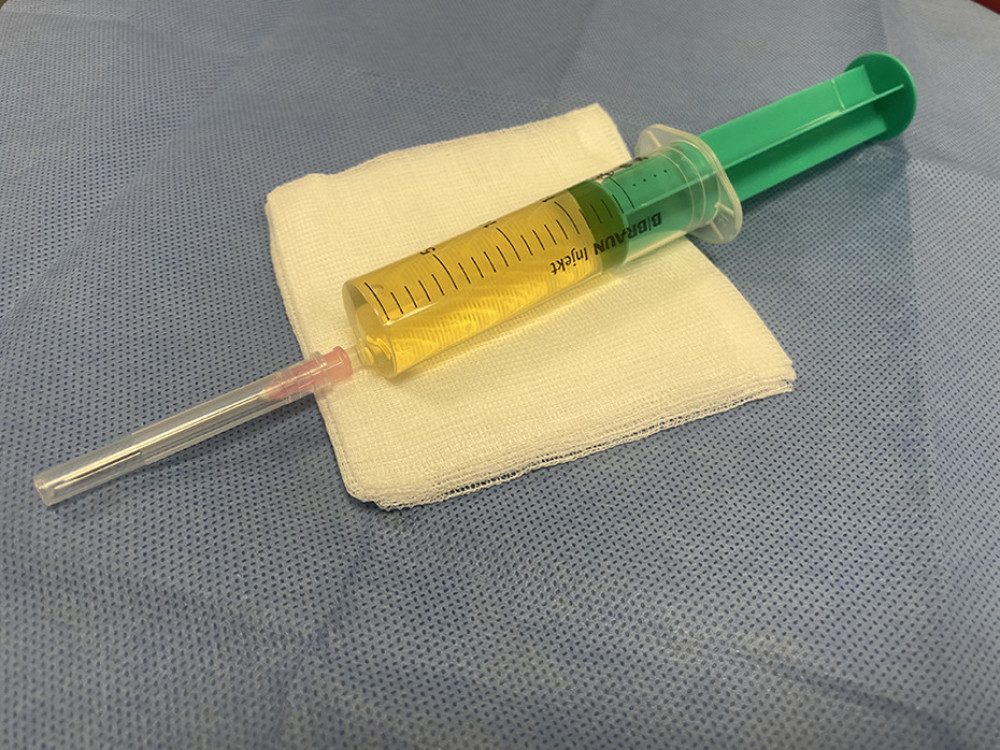
The patient was immediately admitted to the cardiology department with suspected pacemaker pocket infection. Laboratory tests on admission revealed mildly elevated inflammatory markers: C-reactive protein, 24.50 mg/L, and erythrocyte sedimentation rate, 30 mm/hour, with a normal complete blood count (leukocytes, 8.76 × 10³/μL; neutrophils, 7.68 × 10³/μL; lymphocytes, 0.74 × 10³/μL; monocytes, 0.31 × 10³/μL). Aspiration of the pacemaker pocket yielded straw-colored fluid, which was sent for microbiological culture (Figure 1). Given that staphylococcal infections are typically associated with purulent exudate, the appearance of the aspirated fluid may reflect infection with a low-virulence organism or a blunted inflammatory response secondary to impaired host immunity (eg, resulting from corticosteroid therapy or chemotherapy). Blood cultures were also obtained, and empirical antibiotic therapy with intravenous amoxicillin-clavulanic acid (1.2 g every 8 hours) was initiated. Transthoracic echocardiography showed no clinically significant abnormalities, including no pathological findings involving pacemaker leads visualized in the right atrium and right ventricle.
Several days later, microbiological cultures revealed growth of
Although the retrospective history was incomplete, the patient denied recent consumption of undercooked poultry, unpasteurized dairy products, untreated water, or undercooked seafood, as well as contact with pets or farm animals. He also reported no recent diarrhea or other gastrointestinal symptoms.
At 28 days after admission to the cardiology department, a new dual-chamber pacemaker was implanted on the right side. The patient was discharged home on the third postoperative day without signs of local or systemic infection. Since discharge, he has continued regular follow-up at the pacemaker outpatient clinic.
Discussion
Beyond its rarity, this case provides a clinically relevant message: in an immunocompromised patient, even subtle changes in the CIED pocket (eg, swelling or fluid accumulation without erythema, pain, warmth, or purulent discharge) should prompt microbiological evaluation. In the present case,
In our patient, no gastrointestinal symptoms, including diarrhea, abdominal pain, nausea, or vomiting, were reported. Although the primary source of bacteremia could not be definitively established, silent gastrointestinal translocation remains a plausible mechanism. The patient’s immunocompromised status may have contributed to infection onset. Chemotherapy for hematologic malignancy can induce mucosal barrier injury; chronic corticosteroid therapy may impair innate immune responses, including neutrophil migration, macrophage activation, and cytokine signaling [18,19]. Collectively, these mechanisms could theoretically facilitate bloodstream invasion by enteric gram-negative organisms even in the absence of clinically apparent enteritis, although this pathway could not be confirmed in our patient. Thus, subsequent hematogenous seeding of the recently implanted device pocket is a plausible explanation. This interpretation is consistent with observations that gram-negative CIED infections may present more often as isolated pocket infections than as lead-related infective endocarditis [8,9]. The local presentation was atypical. Classical CIED pocket infections—particularly those caused by staphylococci—frequently present with erythema, tenderness, warmth, purulent discharge, wound dehiscence, or device erosion. In contrast, our patient exhibited only pocket swelling and visible subcutaneous fluid accumulation; aspiration yielded straw-colored serous fluid, rather than purulent material. This presentation may reflect the relatively low inflammatory profile of the infection in this anatomical setting, as well as the blunted host inflammatory response associated with chemotherapy and corticosteroid therapy. Accordingly, the absence of classic inflammatory signs should not be considered reassuring in immunocompromised patients with CIEDs.
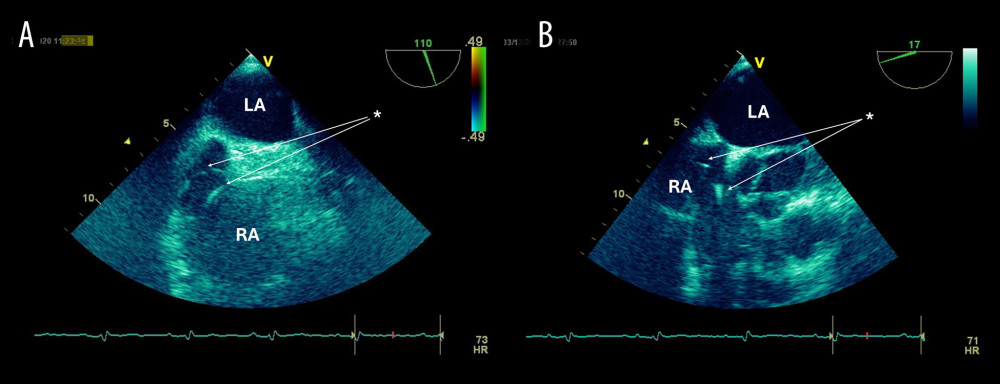
A key management issue in the present case was the interpretation of negative transesophageal echocardiography findings. No vegetations were detected on the pacemaker leads, supporting the diagnosis of pocket infection without definite lead-related infective endocarditis. However, negative transesophageal echocardiography findings do not exclude clinically significant CIED infection when the device pocket is abnormal and positive culture results are observed for both blood and pocket fluid. Current CIED infection management recommendations emphasize that confirmed CIED infection requires complete system removal, including both the generator and leads, because antibiotic therapy alone is associated with a high risk of relapse when infected hardware is retained [5]. Accordingly, complete system extraction was performed despite the absence of echocardiographic vegetations. Microbiological diagnosis was essential for appropriate management.
This report has several limitations typical of a single-case observation. First, the primary source of
Conclusions
CIED infections are most commonly caused by gram-positive bacteria, whereas gram-negative pathogens are rare etiologic agents. The present case demonstrates that
References
1. Birnie DH, Wang J, Alings M, Risk factors for infections involving cardiac implanted electronic devices: J Am Coll Cardiol, 2019; 74(23); 2845-54 [[published erratum appears in J Am Coll Cardiol. 2020;75(7):840–41; J Am Coll Cardiol. 2020;76(6):762]
2. Tarakji KG, Mittal S, Kennergren C, Antibacterial envelope to prevent cardiac implantable device infection: N Engl J Med, 2019; 380(20); 1895-905
3. Clémenty N, Carion PL, Léotoing L, Infections and associated costs following cardiovascular implantable electronic device implantations: A nationwide cohort study: Europace, 2018; 20(12); 1974-80
4. Yang PS, Jeong J, You SJ, The burden and risk factors for infection of transvenous cardiovascular implantable electronic device: A nationwide cohort study: Korean Circ J, 2019; 49(8); 742-52
5. Blomström-Lundqvist C, Traykov V, Erba PA, European Heart Rhythm Association (EHRA) international consensus document on how to prevent, diagnose, and treat cardiac implantable electronic device infections—endorsed by the Heart Rhythm Society (HRS), the Asia Pacific Heart Rhythm Society (APHRS), the Latin American Heart Rhythm Society (LAHRS), International Society for Cardiovascular Infectious Diseases (ISCVID) and the European Society of Clinical Microbiology and Infectious Diseases (ESCMID) in collaboration with the European Association for Cardio-Thoracic Surgery (EACTS): Europace, 2020; 22(4); 515-49
6. Özkartal T, Demarchi A, Conte G, Cardiac implantable electronic devices and bloodstream infections: Management and outcomes: Eur Heart J, 2024; 45(14); 1269-77
7. Han HC, Hawkins NM, Pearman CM, Epidemiology of cardiac implantable electronic device infections: Incidence and risk factors: Europace, 2021; 23(23 Suppl 4); iv3-iv10
8. Schinas G, Koros R, Ntalakouras I, Gram-negative bacterial infections in cardiac implantable electronic devices: Insights from a retrospective analysis of multidrug-resistant and non-multidrug-resistant isolates: Pathogens, 2025; 14(3); 215
9. Polewczyk A, Jacheć W, Segreti L, Bongiorni MG, Kutarski A, Influence of the type of pathogen on the clinical course of infectious complications related to cardiac implantable electronic devices: Sci Rep, 2021; 11(1); 14864
10. Pascale R, Toschi A, Aslan AT, Risk factors for Gram-negative bacterial infection of cardiovascular implantable electronic devices: Multicentre observational study (CarDINe Study): Int J Antimicrob Agents, 2023; 61(3); 106734
11. O’Hara GA, Fitchett JRA, Klein JL, Campylobacter bacteremia in London: A 44-year single-center study: Diagn Microbiol Infect Dis, 2017; 89(1); 67-71
12. Otsuka Y, Hagiya H, Takahashi M: Sci Rep, 2023; 13(1); 647
13. Kemper L, Hensel A: Appl Microbiol Biotechnol, 2023; 107(9); 2725-54
14. Bennett JE, Dolin E, Blaser MJ: Mandell, Douglas, and Bennett’s principles and practice of infectious diseases, 2019, Philadelphia (PA), Elsevier
15. Samuel MC, Vugia DJ, Shallow S: Clin Infect Dis, 2004; 38(Suppl 3); S165-74
16. Feodoroff B, Lauhio A, Ellström P, Rautelin H: Clin Infect Dis, 2011; 53(8); e99-e106
17. Nielsen H, Hansen KK, Gradel KO: Clin Microbiol Infect, 2010; 16(1); 57-61
18. Sonis ST, The pathobiology of mucositis: Nat Rev Cancer, 2004; 4(4); 277-84
19. Blijlevens NMA, Donnelly JP, De Pauw BE, Mucosal barrier injury: Biology, pathology, clinical counterparts and consequences of intensive treatment for haematological malignancy: Bone Marrow Transplant, 2000; 25(12); 1269-78
20. European Food Safety Authority (EFSA); European Centre for Disease Prevention and Control (ECDC), The European Union Summary Report on Antimicrobial Resistance in zoonotic and indicator bacteria from humans, animals and food in 2020/2021: EFSA J, 2023; 21(3); e07867
21. Ioannou P, Sourris A, Tsantes AG, Samonis G: Pathogens, 2024; 13(7); 594
22. Lai T, Yadav R, Schrale R, Mimicking myocardial infarction: localized ST-segment elevation in Campylobacter jejuni myopericarditis: Intern Med J, 2009; 39(6); 422-23
23. Turley AJ, Crilley JG, Hall JA: Resuscitation, 2008; 79(1); 165-67
24. Greenfield GM, Mailey J, Lyons K, Trouton TG: Clin Med (Lond), 2018; 18(1); 98-99
25. Rafi A, Matz J: Ann Allergy Asthma Immunol, 2002; 89(4); 362-67
26. Hannu T, Mattila L, Rautelin H: Eur J Clin Microbiol Infect Dis, 2005; 24(9); 619-22
27. Bessède E, Lehours P, Labadi L: J Clin Microbiol, 2014; 52(1); 328-30
In Press
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953909
Case report
Am J Case Rep In Press; DOI: 10.12659/AJCR.952933
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954126
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.952879
Most Viewed Current Articles
07 Dec 2021 : Case report
24,785,731
DOI :10.12659/AJCR.934347
Am J Case Rep 2021; 22:e934347
06 Dec 2021 : Case report  179,635
DOI :10.12659/AJCR.934406
Am J Case Rep 2021; 22:e934406
21 Jun 2024 : Case report
123,411
DOI :10.12659/AJCR.944371
Am J Case Rep 2024; 25:e944371
07 Mar 2024 : Case report
67,810
DOI :10.12659/AJCR.943133
Am J Case Rep 2024; 25:e943133