


12 September 2026: Articles 
Recurrent Intravenous Contrast-Induced Submandibular Sialadenitis: A Case Report and Literature Review
Unknown etiology, Challenging differential diagnosis, Diagnostic / therapeutic accidents, Unusual setting of medical care, Unexpected drug reaction, Educational Purpose (only if useful for a systematic review or synthesis)
Narisara Chobaroon ABCDEF 1, Thitiporn Suwatanapongched ACDEF 1*DOI: 10.12659/AJCR.953439
Am J Case Rep 2026; 27:e953439


Abstract
BACKGROUND: Iodinated contrast-induced sialadenitis (iodide mumps) is a rare and underrecognized delayed non-allergic adverse reaction to iodinated contrast media. It is characterized by painless or painful swelling of 1 or more salivary glands, typically occurring several hours after contrast exposure.
CASE REPORT: A 75-year-old Thai woman with stage 3a chronic kidney disease was referred for contrast-enhanced chest computed tomography (CT) imaging to evaluate longstanding bronchiectasis. Because she reported a prior episode of bilateral neck and submandibular swelling shortly after intravenous contrast administration 10 years earlier, premedication with oral prednisolone was prescribed. However, with a delayed onset (16 hours) after intravenous administration of iopromide (370 mg I/mL), she developed painful bilateral submandibular swelling and returned to the hospital. Physical examination revealed firm, mildly tender bilateral submandibular swelling without overlying erythema or purulent discharge from the openings of Wharton’s ducts. No laryngeal edema or bronchospasm was observed. Ultrasonography demonstrated diffuse enlargement of both submandibular glands, with heterogeneous echotexture, increased vascularity, and mild intraglandular ductal dilatation, without evidence of sialolithiasis or abscess. Based on the characteristic sonographic findings and the temporal relationship with contrast administration, a diagnosis of recurrent iodinated contrast-induced bilateral submandibular sialadenitis after re-exposure was made. Conservative management with warm compresses and oral analgesics resulted in complete symptom resolution within 4 days.
CONCLUSIONS: Iodinated contrast-induced sialadenitis is a rare, self-limited delayed reaction to iodinated contrast media that can recur after re-exposure. Recognition of its characteristic clinical and imaging findings is important to aid diagnosis and avoid misdiagnosis and unnecessary contrast exposure, premedication, investigations, and treatment.
Keywords: Contrast Media, Iodides, mumps, Recurrence, Sialadenitis
Introduction
Iodinated contrast media are widely used in diagnostic imaging, including contrast-enhanced computed tomography (CT) and interventional vascular procedures such as coronary angiography. Adverse reactions to intravascular iodinated contrast media are generally classified as acute (immediate) or delayed [1]. Acute reactions, which can be allergic-like or physiologic, are well-recognized adverse events, with reported incidence rates of approximately 0.2% to 3.1% with modern nonionic low-osmolar contrast agents [1–5]. These reactions are typically graded as mild, moderate, or severe [1]. Premedication is recommended for individuals with a prior moderate or severe reaction [1].
Delayed adverse reactions are often underrecognized, despite occurring in approximately 0.5% to 3% of patients receiving modern nonionic contrast media [1,6,7]. Prospective data suggest higher rates of up to 14% in some series [8]. These reactions most commonly manifest as cutaneous eruptions, such as maculopapular rash, urticaria, and angioedema [6–8].
Another rare and underrecognized delayed non-allergic reaction is iodinated contrast-induced sialadenitis, also known as iodide mumps, first described by Miller and Sussman in 1956 [9]. The condition is characterized by transient, painless or painful enlargement of the salivary glands, most commonly involving the submandibular and parotid glands [10].
The pathogenesis of iodinated contrast-induced sialadenitis remains incompletely understood. One proposed mechanism is transient accumulation of iodide within the salivary glands following contrast administration, resulting in glandular swelling [10–13]. Impaired renal function has been proposed as a potential contributing factor, although a definitive association has not been established [10,14–16].
Iodinated contrast-induced sialadenitis remains underrecognized and has been reported predominantly in isolated case reports and small case series, with no large prospective studies available [10,11,14–16]. The true incidence and prevalence of this condition have not been established. More recently, additional cases have continued to be reported in the literature, underscoring that this uncommon condition remains relevant in contemporary clinical practice [17–20]. Within this limited body of evidence, recurrence following re-exposure appears to be uncommon, with fewer than 10 cases described [16,19,21–24] and remains incompletely characterized in terms of clinical patterns and imaging findings.
Herein, we report a case of recurrent iodinated contrast-induced bilateral submandibular sialadenitis to further characterize this underrecognized condition, with emphasis on key clinical and imaging features—particularly the delayed onset following contrast exposure—and to inform considerations regarding recurrence after re-exposure despite corticosteroid premedication given for a presumed allergic reaction. These observations may aid diagnosis and differentiation from other causes of acute salivary gland swelling and underscore the importance of awareness of this condition to avoid misdiagnosis and unnecessary contrast exposure, premedication, investigations, and treatments.
Case Report
A 75-year-old Thai woman with stage 3a chronic kidney disease was referred for contrast-enhanced chest CT to evaluate longstanding bronchiectasis prior to bronchoscopy because of progressive productive cough for 3 months. She reported a prior episode of bilateral neck and submandibular swelling shortly after intravenous contrast administration in 2015, which resolved completely without sequelae. Although the event was not documented in her current electronic medical record, archival radiology records subsequently identified the culprit agent as iopromide (370 mg I/mL) intravenous injection. Specific details regarding the administered volume, injection rate, precise onset of symptoms, and management were unavailable. She denied tobacco smoking, alcohol consumption, or substance abuse. Therefore, premedication according to the institutional protocol was administered, consisting of oral prednisolone 50 mg at 13 hours, 7 hours, and 1 hour before the CT examination.
At the time of the CT examination, the patient weighed 41 kg and was 154 cm tall. Her serum creatinine level was 1.02 mg/dL, with an estimated glomerular filtration rate of 54.9 mL/min/1.73 m2, consistent with stage 3a chronic kidney disease. Contrast-enhanced chest CT was performed following intravenous administration of 55 mL of iopromide (370 mg iodine/mL), corresponding to a weight-based dose of 1.34 mL/kg, via an antecubital vein at an injection rate of 1.8 mL/s using a power injector.
No immediate adverse reaction was observed. Approximately 3 hours after returning home from the examination, she developed facial flushing and dizziness. Painful bilateral submandibular swelling subsequently developed about 16 hours after contrast administration. The pain was aggravated by drinking hot water, prompting her to return to the hospital approximately 18 hours after receiving the contrast agent.
On physical examination, firm and tender bilateral submandibular swelling was noted (Figure 1), without overlying erythema or purulent discharge from the openings of Wharton’s ducts. The patient remained afebrile and hemodynamically stable, with no evidence of systemic distress, airway compromise, laryngeal edema, or bronchospasm.
Ultrasonographic evaluation of the salivary glands demonstrated diffuse enlargement of both submandibular glands, with mild heterogeneous echotexture and mild intraglandular ductal dilatation (Figure 2A, 2B). Color Doppler ultrasound showed moderately increased parenchymal vascularity, most prominent in the central portion of the submandibular glands and slightly greater on the right (Figure 2C, 2D). Bilateral parotid glands were normal (Figure 3). No obstructive sialolithiasis or focal abscess formation was identified.
Based on the characteristic sonographic findings and the temporal relationship with recent contrast administration, recurrent intravenous contrast-induced bilateral submandibular sialadenitis was diagnosed. Conservative management, including warm compresses applied to the submandibular glands and oral analgesics, including a single dose of naproxen 200 mg on the first day of symptoms, was instituted. The swelling and glandular enlargement improved markedly by day 4 after symptom onset. A follow-up examination on day 7 confirmed complete resolution of the bilateral submandibular swelling, with no residual pain or discomfort (Figure 4).
Discussion
This case contributes to the limited evidence on recurrent iodinated contrast-induced sialadenitis (iodide mumps), a rare and underrecognized delayed adverse reaction to iodinated contrast media, and highlights several clinically relevant points. In line with previous reports, the patient had a typical clinical course characterized by transient, non-suppurative enlargement of 1 or more salivary glands with delayed onset approximately 16 hours after contrast administration, consistent with the reported onset range from a few minutes to 5 days (median, ~ 16 hours) [10]. The submandibular and parotid glands are most commonly involved [10,11].
Recurrence after re-exposure has been described with both ionic and nonionic contrast agents across different classes [16,19,21–24]. Although the true frequency remains uncertain, the condition appears to be rare and is probably underrecognized in routine clinical practice. Limited awareness may lead to misinterpretation as an allergic reaction, infection, or obstructive salivary gland disease [10,11,16,19–23]. While generally painless, recurrent episodes can present with pain, as observed in this case and in prior reports [16,21].
Given the broad differential diagnosis of submandibular gland enlargement, identifying the underlying cause can be challenging. In this clinical context, life-threatening conditions such as angioedema, which can occur as a severe allergic reaction to contrast media, must first be excluded [1,2,5,6]. In the present case, the delayed onset of symptoms, together with the absence of urticaria, airway compromise, or hemodynamic instability, made angioedema unlikely.
Infectious etiologies are another important consideration in patients presenting with acute painful salivary gland swelling. Viral infections, particularly mumps, typically present with systemic symptoms and a progressively worsening clinical course. Suppurative bacterial sialadenitis—most commonly caused by
To evaluate the likelihood of an adverse drug reaction after intravenous contrast media exposure, the Naranjo algorithm was applied [27]. Our patient achieved a score of 9, indicating a definite adverse drug reaction according to the Naranjo probability scale. Furthermore, no concurrent medication exposure or underlying comorbidity was identified as a more likely alternative cause of the recurrent bilateral submandibular sialadenitis. Although she had chronic kidney disease, this condition is considered a potential contributing factor rather than a more plausible alternative diagnosis.
In this regard, imaging plays an important role in distinguishing iodinated contrast-induced sialadenitis from other causes of salivary gland enlargement. Ultrasonography is the preferred first-line imaging modality for evaluating salivary gland pathology [26]. Obstructive causes, particularly sialolithiasis, should be considered in the differential diagnosis. These conditions typically present with unilateral gland swelling and demonstrate dilatation of the excretory duct—most commonly Wharton’s duct in the submandibular gland—proximal to an intraductal echogenic calculus with posterior acoustic shadowing on ultrasound [26]. Sialosis, which is usually associated with metabolic or endocrine disorders, can also present with gland enlargement; however, its sonographic appearance typically shows diffuse hyperechogenic enlargement without Doppler hyperemia [11,25].
Characteristic sonographic findings of iodinated contrast-induced sialadenitis include diffuse enlargement of the affected salivary glands, with heterogeneous parenchymal echotexture, mild intraglandular ductal dilatation, and increased vascularity on color Doppler imaging, without evidence of obstructive sialolithiasis [10,11]. These findings, similar to those in the present case, together with the delayed onset following contrast administration, support the diagnosis. In selected reports, CT demonstrates diffuse gland enlargement with decreased attenuation consistent with edema, without evidence of calculi or abscess formation [12,28,29].
The pathogenesis of iodinated contrast-induced sialadenitis remains incompletely understood. Impaired renal function may contribute from a mechanistic standpoint. Approximately 98% of administered iodine is eliminated by renal excretion, whereas a small fraction is excreted through exocrine pathways, including the salivary glands. Because salivary glands can concentrate iodide to levels substantially higher than plasma levels, delayed renal clearance can increase salivary iodide exposure, potentially leading to transient ductal edema and glandular swelling [13]. This mechanism may partly explain the occurrence of this condition in patients with chronic kidney disease, as in the present case, as well as in those undergoing hemodialysis [13–19,21].
However, clinical evidence supporting a causal relationship remains inconclusive. A meta-analysis of 77 published cases found no significant association between iodinated contrast-induced sialadenitis and renal function, despite approximately 35% of patients having impaired renal function [10]. Additionally, reported cases in patients undergoing hemodialysis illustrate that the condition can occur in the setting of renal dysfunction, but do not establish causality [10,14–16,19]. These findings suggest that renal impairment alone is unlikely to be the sole determinant.
Other proposed factors have also been evaluated. In particular, contrast media osmolarity has not demonstrated a consistent or clinically meaningful association with the occurrence or severity of iodinated contrast-induced sialadenitis. Similarly, treatment-related factors, including corticosteroids, antihistamines, or dialysis, have not shown a clear impact on clinical course or recurrence [10,16]. Alternative mechanisms have therefore been proposed, including direct toxic glandular injury with increased vascular permeability (vasogenic edema) and non–IgE-mediated pseudoallergic reactions [10,12].
In the present case, recurrence occurred despite corticosteroid premedication given for a presumed allergic reaction, indicating that premedication did not prevent recurrence in this instance. This observation is based on a single case and cannot be generalized. At the population level, a meta-analysis and literature review found no significant association between this condition and treatment modalities, including corticosteroids, antihistamines, or dialysis [10,16]. However, these findings are derived predominantly from case reports, case series, and limited systematic reviews and meta-analyses, and the effectiveness of preventive strategies cannot be definitively established in the absence of prospective data.
Because the condition is usually self-limited, management of iodinated contrast-induced sialadenitis is primarily conservative [10]. Most cases resolve spontaneously within several days (median, approximately 3 days) and typically do not require specific treatment, as demonstrated in the present case. Nevertheless, rare severe presentations associated with significant cervical swelling and potential airway compromise have been reported in the literature [30]. Consequently, careful clinical assessment is warranted to exclude airway involvement, particularly in patients presenting with extensive cervical swelling.
Awareness of this condition, particularly its potential for recurrence following re-exposure, is important to avoid unnecessary repeat contrast exposure, as well as unnecessary premedication, investigations, and antibiotic therapy [10]. Although no statistically significant association between iodinated contrast-induced sialadenitis and renal function has been demonstrated [10], clinicians should remain aware that this condition has been reported in patients with chronic kidney disease or impaired renal clearance of iodide [14,18,20]. Therefore, a history of prior iodinated contrast-induced sialadenitis should be carefully considered before repeat contrast administration.
Conclusions
This case highlights key clinical and imaging features, as well as management considerations, of recurrent iodinated contrast-induced sialadenitis in a patient with chronic kidney disease. The characteristic delayed onset, temporal relationship with contrast administration, and sonographic findings aid diagnosis and differentiate this condition from allergic reactions, infection, and obstructive salivary gland disease.
In the absence of established preventive strategies, awareness of this generally self-limited condition among radiologists, radiologic technologists, interventionalists, and referring clinicians is important to avoid misdiagnosis and unnecessary premedication, investigations, and treatment, and to facilitate appropriate patient reassurance. Although current evidence does not support a definitive association with chronic kidney disease, when clinically feasible, alternative imaging strategies may be considered in patients with a prior history of this condition to minimize repeat contrast exposure.
Figures
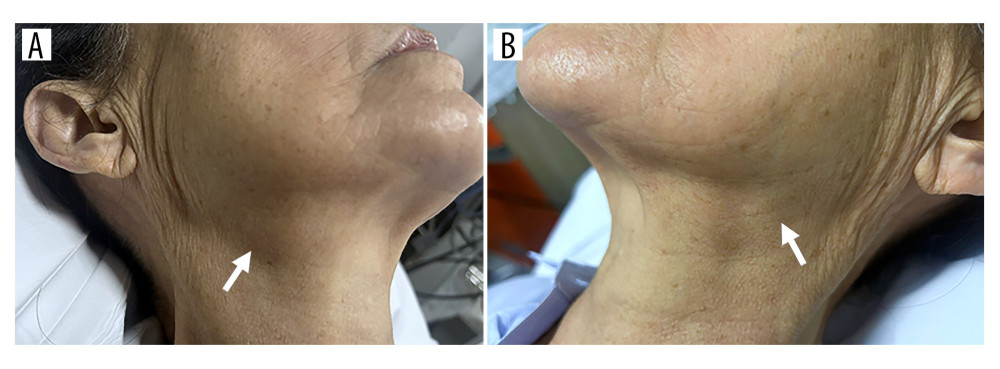 Figure 1. Clinical photographs obtained 18 hours after intravenous iodinated contrast administration demonstrate asymmetric swelling of the submandibular regions, more pronounced on the right (A) than on the left (B) (arrows).
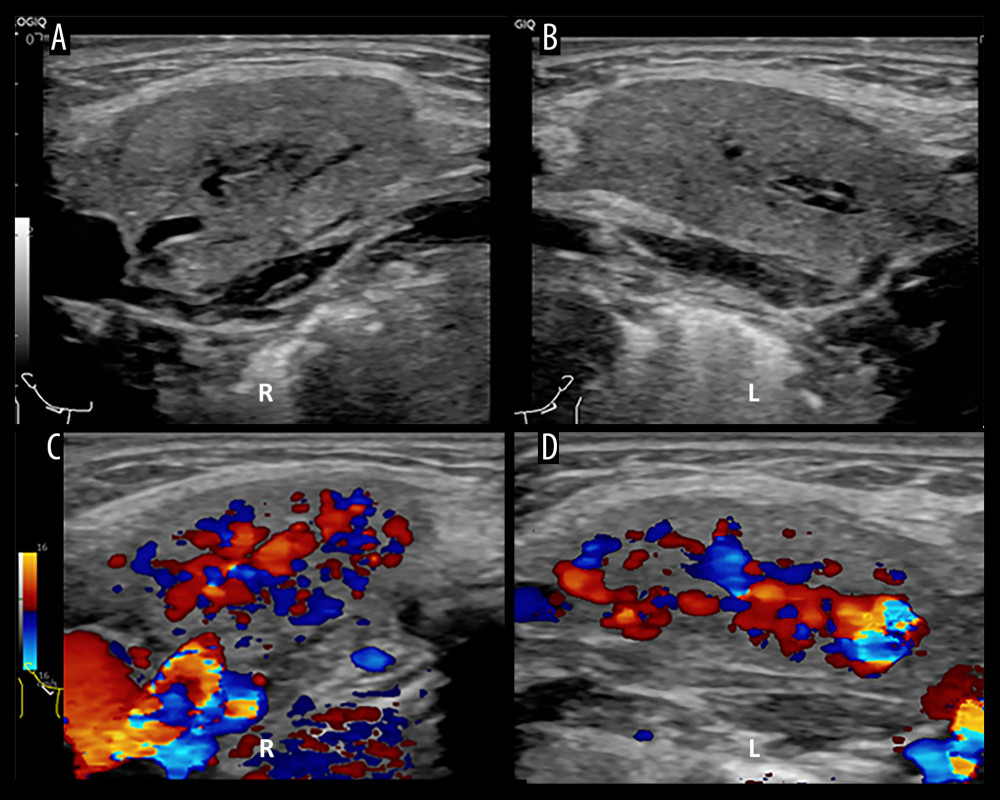 Figure 2. Ultrasonographic images of the submandibular glands obtained 18 hours after contrast administration. (A, B) Gray-scale images of the right (A) and left (B) submandibular glands demonstrate mild heterogeneous parenchymal echotexture with mild intraglandular ductal dilatation. (C, D) Color Doppler images demonstrate increased parenchymal vascularity within the right (C) and left (D) submandibular glands.
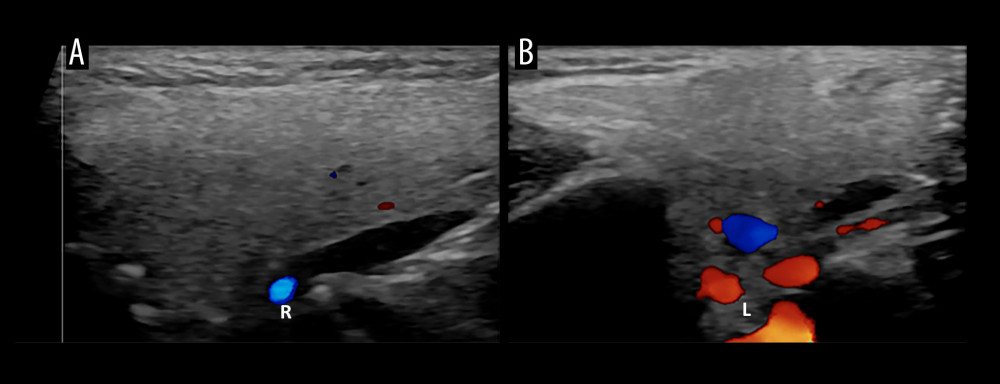 Figure 3. Color Doppler ultrasonographic images of the right (A) and left (B) parotid glands demonstrate homogeneous parenchymal echotexture without abnormal vascularity.
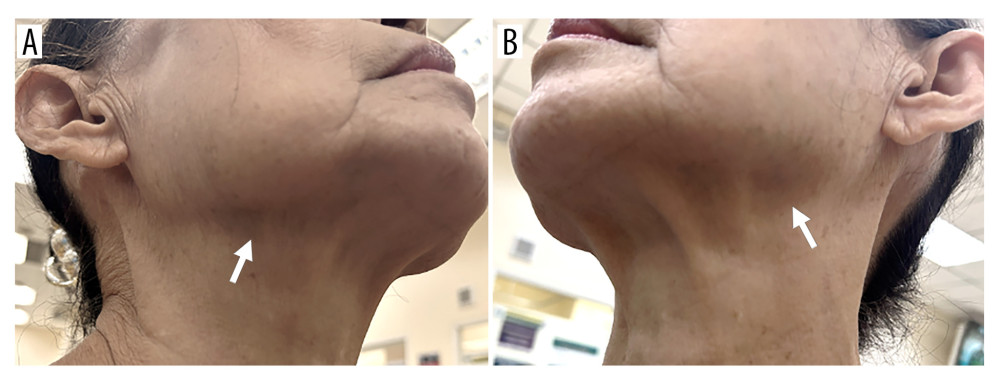 Figure 4. Follow-up clinical photographs obtained 7 days later demonstrate complete resolution of the previously noted swelling in the right (A) and left (B) submandibular regions (arrows).
References
1. Meth MJ, Maibach HI, Current understanding of contrast media reactions and implications for clinical management: Drug Saf, 2006; 29(2); 133-41
2. Katayama H, Yamaguchi K, Kozuka T, Adverse reactions to ionic and nonionic contrast media. A report from the Japanese Committee on the Safety of Contrast Media: Radiology, 1990; 175(3); 621-28
3. Cochran ST, Bomyea K, Sayre JW, Trends in adverse events after IV administration of contrast media: Am J Roentgenol, 2001; 176(6); 1385-88
4. Mortele KJ, Oliva MR, Ondategui S, Universal use of nonionic iodinated contrast medium for CT: Evaluation of safety in a large urban teaching hospital: Am J Roentgenol, 2005; 184(1); 31-34
5. Wang CL, Cohan RH, Ellis JH, Frequency, outcome, and appropriateness of treatment of nonionic iodinated contrast media reactions: Am J Roentgenol, 2008; 191(2); 409-15
6. Torres MJ, Trautmann A, Bohm I, Practice parameters for diagnosing and managing iodinated contrast media hypersensitivity: Allergy, 2021; 76(5); 1325-39
7. Christiansen C, Pichler WJ, Skotland T, Delayed allergy-like reactions to X-ray contrast media: Mechanistic considerations: Eur Radiol, 2000; 10(12); 1965-75
8. Loh S, Bagheri S, Katzberg RW, Delayed adverse reaction to contrast-enhanced CT: A prospective single-center study comparison to control group without enhancement: Radiology, 2010; 255(3); 764-71
9. Miller J, Sussman RM, Iodide mumps after intravenous urography: N Engl J Med, 1956; 255(9); 433-34
10. Jiao A, Farsad K, McVinnie DW, Characterization of iodide-induced sialadenitis: Meta-analysis of the published case reports in the medical literature: Acad Radiol, 2020; 27(3); 428-35
11. Lucarelli A, Perandini S, Borsato A, Iodinated contrast-induced sialadenitis: A review of the literature and sonographic findings in a clinical case: J Ultrason, 2018; 18(75); 359-64
12. Zhang G, Li T, Wang H, Liu J, The pathogenesis of iodide mumps: A case report: Medicine (Baltimore), 2017; 96; e8881
13. Talner LB, Lang JH, Brasch RC, Lasser EC, Elevated salivary iodine and salivary gland enlargement due to iodinated contrast media: Am J Roentgenol Radium Ther Nucl Med, 1971; 112(2); 380-82
14. Ghosh RK, Somasundaram M, Ravakhah K, Iodide mumps following fistulogram in a haemodialysis patient: BMJ Case Rep, 2016; 2016; bcr2015214037
15. Braslavsky GJ, Taylor MF, Malinar M, Miranda F, Contrast-induced sialadenitis in a patient with chronic renal failure: Rev Nefrol Dial Traspl, 2020; 40(1); 80-89
16. Zhang G, Li Y, Zhang R, Acute submandibular swelling complicating arteriography with iodide contrast: A case report and literature review: Medicine (Baltimore), 2015; 94(33); e1380
17. Mansour FA, Habib PK, El Haddad BN, Joubran NI, The Case | Bilateral submandibular swelling in a dialysis patient: Kidney Int, 2021; 100(1); 251-52
18. Gergis M, Wagdy K, Elborae A, Elguindy A, Contrast-induced sialadenitis: A forgotten complication of coronary angiography: JACC Case Rep, 2022; 4(23); 01653
19. Georgery H, Lengele JP, Leflot S, Gillion V, Recurrent iodine-induced sialadenitis in a patient undergoing hemodialysis: Is this really ineluctable?: Kidney Int, 2024; 106(5); 997
20. Deolankar M, Gore K, Gottlieb M, Contrast-induced sialadenitis: Clin Exp Emerg Med, 2025; 12(4); 416-17
21. Ben-Ami R, Zeltser D, Herz I, Mardi T, Iodide-induced sialadenitis complicating coronary angiography: Catheter Cardiovasc Interv, 2002; 57(1); 50-53
22. Wyplosz B, Scotte F, Lillo-Le Louet A, Chevrot A, Recurrent iodide mumps after repeated administration of contrast media: Ann Intern Med, 2006; 145(2); 155-56
23. Gilgen-Anner Y, Heim M, Ledermann HP, Bircher AJ, Iodide mumps after contrast media imaging: A rare adverse effect to iodine: Ann Allergy Asthma Immunol, 2007; 99(1); 93-98
24. Wilhelmi M, Gasser SRecurrent parotid enlargement following coronary angiography: Praxis (Bern 1994), 2008; 97(10); 569-70 [in German]
25. Adhikari R, Soni A, Submandibular sialadenitis and sialadenosis: StatPearls [Internet], 2026, Treasure Island (FL), StatPearls Publishing
26. Benito DA, Badger C, Hoffman HT, Joshi A, Recommended imaging for salivary gland disorders: Curr Otorhinolaryngol Rep, 2020; 8; 311-20
27. Naranjo CA, Busto U, Sellers EM, A method for estimating the probability of adverse drug reactions: Clin Pharmacol Ther, 1981; 30(2); 239-45
28. Bohora S, Harikrishnan S, Tharakan J, Iodide mumps: Int J Cardiol, 2008; 130(1); 82-83
29. Afshar M, Alhussein M, Iodide-associated sialadenitis: N Engl J Med, 2017; 376(9); 868
30. Paauw HM, Mayasi Y, Iodine-induced sialadenitis requiring intubation after intracranial venous sinus stenting: A case report: Am J Case Rep, 2026; 27; e949986
Figures
Figure 1. Clinical photographs obtained 18 hours after intravenous iodinated contrast administration demonstrate asymmetric swelling of the submandibular regions, more pronounced on the right (A) than on the left (B) (arrows).Figure 2. Ultrasonographic images of the submandibular glands obtained 18 hours after contrast administration. (A, B) Gray-scale images of the right (A) and left (B) submandibular glands demonstrate mild heterogeneous parenchymal echotexture with mild intraglandular ductal dilatation. (C, D) Color Doppler images demonstrate increased parenchymal vascularity within the right (C) and left (D) submandibular glands.Figure 3. Color Doppler ultrasonographic images of the right (A) and left (B) parotid glands demonstrate homogeneous parenchymal echotexture without abnormal vascularity.Figure 4. Follow-up clinical photographs obtained 7 days later demonstrate complete resolution of the previously noted swelling in the right (A) and left (B) submandibular regions (arrows). In Press
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.952499
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953531
Case report
Am J Case Rep In Press; DOI: 10.12659/AJCR.953461
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954251
Most Viewed Current Articles
07 Dec 2021 : Case report  22,774,712
DOI :10.12659/AJCR.934347
Am J Case Rep 2021; 22:e934347
06 Dec 2021 : Case report  179,275
DOI :10.12659/AJCR.934406
Am J Case Rep 2021; 22:e934406
21 Jun 2024 : Case report
123,110
DOI :10.12659/AJCR.944371
Am J Case Rep 2024; 25:e944371
07 Mar 2024 : Case report
67,547
DOI :10.12659/AJCR.943133
Am J Case Rep 2024; 25:e943133