


22 September 2026: Articles 
Dual-Site Postsurgical Pyoderma Gangrenosum of the Breast and Back With Delayed Diagnosis: A Case Report
Unusual clinical course, Challenging differential diagnosis
Tristan Packard ABCDEF 1*, Grant Dolan ABCD 2, Cathryn Chance BEF 1, Mark Jones ABDE 3DOI: 10.12659/AJCR.954079
Am J Case Rep 2026; 27:e954079


Abstract
BACKGROUND: Postsurgical pyoderma gangrenosum is a rare neutrophilic dermatosis that can mimic infection, wound dehiscence, malignancy, foreign-body reaction, or impaired surgical healing. Diagnostic delay is common and may lead to repeated debridement, which can worsen ulceration through pathergy. This case highlights the diagnostic challenge of multifocal postsurgical pyoderma gangrenosum involving anatomically distinct sites after procedures initially performed for presumed benign lesions.
CASE REPORT: A 70-year-old woman with celiac disease and prior left breast cancer treated with lumpectomy, chemotherapy, radiation, and implant reconstruction developed nonhealing ulcers of the left superior breast and left lower back after surgical treatment of benign lesions. Initial evaluation favored retained cyst lining, foreign-body reaction, infection, impaired wound healing, and possible implant-related complications. Despite advanced wound therapies, antimicrobials, and biologic wound products, both lesions progressively enlarged. Biopsies demonstrated abscess formation, multinucleated giant cells, and sinus tract formation without malignancy. Wound cultures and pulmonary findings complicated the diagnostic course, but neither targeted antimicrobial nor prolonged antifungal therapy produced sustained improvement. The diagnosis was clinically supported by worsening after procedural intervention, exclusion of malignancy and persistent infection, multifocal involvement, and rapid response after initiation of topical and intralesional corticosteroid therapy.
CONCLUSIONS: This case supports considering postsurgical pyoderma gangrenosum in refractory postsurgical wounds that worsen despite local wound-directed interventions, particularly when lesions involve multiple anatomically distinct surgical sites. The complete resolution of both lesions after topical and intralesional corticosteroid therapy further supports the importance of recognizing an inflammatory, pathergy-driven process once infection, malignancy, and other local causes have been reasonably excluded. Earlier recognition may help avoid repeated procedural trauma, unnecessary treatment escalation, and prolonged morbidity.
Keywords: Pyoderma Gangrenosum, Wound Healing, Breast Diseases, Case Reports
Introduction
Postsurgical pyoderma gangrenosum (PSPG) is a rare but increasingly recognized neutrophilic dermatosis occurring at surgical sites, with breast surgery being a common trigger [1,2]. A systematic review identified only 220 published PSPG cases from 1946 to 2013, underscoring the rarity of this postoperative complication [3]. Diagnosis is frequently delayed due to clinical mimicry of wound infection, dehiscence, or necrosis. In 1 case series, the mean time to diagnosis was 14.8 ± 6.6 days [2]. Delayed recognition may lead to prolonged antimicrobial therapy, repeated procedural intervention, or inappropriate debridement, which can trigger pathergy, the paradoxical worsening of wounds following trauma, and progressive ulceration [2,4,5]. Multifocal involvement of anatomically distinct surgical sites may be clinically important because it can prompt earlier reconsideration of PSPG when separate postoperative wounds worsen despite antimicrobial therapy and local wound-directed interventions. We present this case as an incremental clinical report of postsurgical pyoderma gangrenosum with an unusually prolonged diagnostic delay and involvement of 2 anatomically distinct postoperative sites, illustrating a practical diagnostic challenge in which progressive multifocal wound enlargement after surgery should prompt reconsideration of pyoderma gangrenosum.
Case Report
A 70-year-old woman with celiac disease and prior left breast cancer (treated with lumpectomy, chemotherapy, and radiation followed by implant reconstruction) presented in early 2024 with 2 nonhealing ulcers: 1 on the left superior breast and 1 on the left lower back. On initial surgical evaluation, the breast lesion was described as a partially necrotic, draining ulcer without surrounding erythema, while the lower back lesion demonstrated persistent drainage with surrounding erythema and inflammation extending beyond the wound margin. Both developed following surgical excision of presumed benign lesions, a sebaceous cyst on the breast and an abscess on the back.
Initial surgical evaluation attributed nonhealing to retained cyst lining and foreign-body reaction. Formal excision of both sites revealed deep dermal ulceration with reactive fibrosis and fat necrosis, without malignancy. The breast specimen demonstrated extensive tissue destruction: ulceration with a fissure extending 1.5 cm deep, indurated hemorrhagic tissue, and calcification at the deep margin. The lesion on the patient’s back healed, whereas the breast lesion remained persistent.
The patient entered specialized wound care several months after initial presentation for management of a chronic nonhealing breast ulcer. Treatment included hyperbaric oxygen therapy, serial debridement, and advanced biologic dressings (human amniotic membrane, collagen-based wound matrices, and fish-skin–derived grafts). Despite these interventions, the breast lesion progressively enlarged over several weeks, increasing from approximately 1.0 × 3.0 cm to 2.0 × 3.0 cm and ultimately 4.5 × 3.5 cm following repeated debridement (Figure 1A, 1B). Shortly after receiving treatment for her breast wound, the wound on her back reopened, initially measuring 0.2 × 0.5 cm and increasing to 0.9 × 1.2 cm (Figure 2A, 2B). The recurrence and progressive enlargement of the back lesion occurred while the breast lesion was also worsening, creating a multifocal pattern of nonhealing ulceration.
However, a diagnostic detour occurred when concurrent pulmonary imaging revealed a right lower lobe mass with mediastinal lymphadenopathy. Bronchoscopy demonstrated necrotizing granulomatous inflammation with yeast forms on histology, leading to a presumed diagnosis of disseminated blastomycosis, and itraconazole therapy was initiated. Unfortunately, after more than 6 months of antifungal treatment, there was no improvement in either wound, arguing against a primary infectious etiology.
Further evaluation revealed elevated inflammatory markers (ESR 48) and a positive antinuclear antibody, though extensive autoimmune and hematologic workup was otherwise unrevealing. Repeat biopsy of the breast and back lesions demonstrated dermal abscess formation with multinucleated giant cells and sinus tract formation, without evidence of malignancy. Wound cultures intermittently grew
By early 2025, after nearly 50 weeks of treatment without resolution, postsurgical pyoderma gangrenosum became the favored diagnostic consideration. Although formal dermatology consultation was not established, this diagnostic shift was based on the progressive multifocal wound enlargement, lack of sustained response to antimicrobial and antifungal therapy, and exclusion of malignancy. At this point, the patient’s breast lesion measured 10.0 × 10.5 cm (Figure 1C), and the patient’s back lesion measured 2.0 × 2.5 cm (Figure 2C).
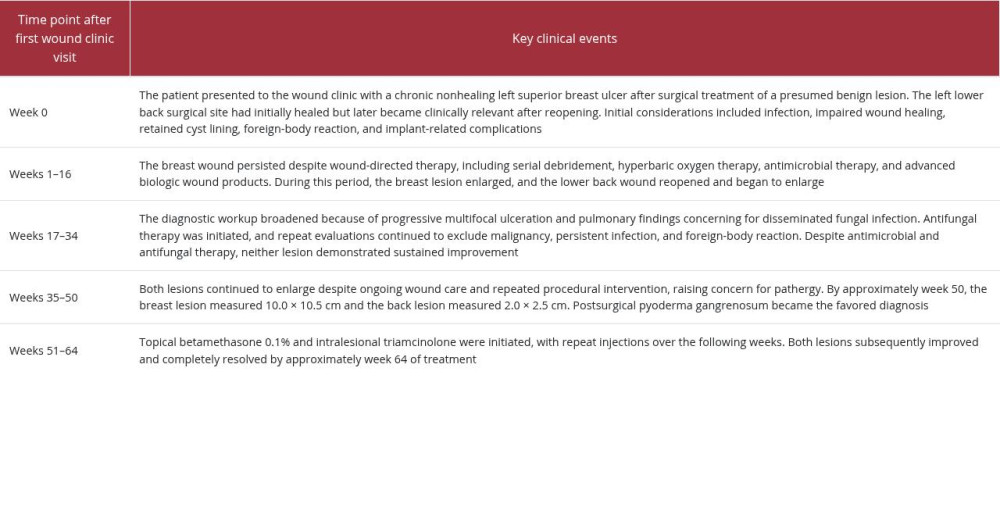
This diagnostic shift prompted targeted immunosuppressive therapy. Given the localized distribution of the lesions, ongoing diagnostic uncertainty, and concurrent infectious considerations, topical betamethasone 0.1% and intralesional triamcinolone were selected to provide targeted anti-inflammatory therapy while limiting systemic immunosuppression, with repeat injections administered over the subsequent several weeks. Human amnion/chorion membrane allograft had been applied prior to the initiation of steroid therapy without sustained improvement and was subsequently continued as adjunctive treatment. The clinical response was rapid and marked, with complete resolution of both lesions by week 64 of treatment (Figures 1D, 2D), supporting an underlying inflammatory etiology. A summary of the clinical course after initial wound clinic evaluation is provided in Table 1.
Discussion
RECOGNIZE PATHERGY EARLY:
Wound enlargement after debridement or surgical procedures should immediately trigger consideration of PSPG, regardless of prior working diagnoses. Our patient’s breast wound surface area increased from approximately 3 cm2 to nearly 16 cm2 despite serial debridement, representing more than a 5-fold increase. Although this finding is not diagnostic in isolation, progressive wound enlargement after repeated procedural intervention is a strong clinical clue for pathergy [4,6]. In retrospect, the reopening and progressive enlargement of a second anatomically distinct wound should have prompted earlier reconsideration of the primary diagnosis, particularly given the concurrent worsening of the breast lesion despite repeated local wound-directed interventions.
AVOID DEBRIDEMENT IN SUSPECTED PYODERMA GANGRENOSUM:
A 2024 retrospective cohort study of 104 pyoderma gangrenosum patients demonstrated that debridement significantly decreased remission rates (adjusted HR 0.45, 95% CI 0.26–0.78) and increased disease progression (68% vs 15% in non-debrided patients) [4]. The Mayo Clinic experience documented that 61% of PSPG patients underwent debridement before diagnosis [5]. Our case reinforces this evidence: wound resolution occurred only after debridement was stopped and immunosuppression initiated.
APPLY DIAGNOSTIC CRITERIA SYSTEMATICALLY BUT RECOGNIZE THEIR LIMITATIONS:
The 2018 Delphi consensus criteria for ulcerative pyoderma gangrenosum require 1 major criterion, biopsy showing a neutrophilic infiltrate, plus ≥ 4 of 8 minor criteria, to achieve 86% sensitivity and 90% specificity [7]. Notably, our patient’s biopsies demonstrated abscess formation, multinucleated giant cells, and sinus tract formation rather than a clearly documented neutrophilic infiltrate, meaning the major criterion was not definitively met. The patient did satisfy multiple minor criteria, including exclusion of infection, pathergy, history of autoimmune disease, multiple ulcerations, peripheral erythema, and response to immunosuppression, yet incomplete fulfillment of the Delphi framework may have contributed to the prolonged diagnostic delay. This case illustrates that consensus criteria should be applied alongside clinical judgment, particularly when progressive postsurgical ulceration, multifocal involvement, and worsening after procedural intervention raise suspicion for pyoderma gangrenosum despite nonspecific or incomplete histopathologic findings. This approach is supported by comparative diagnostic data from Haag et al [8], who found that commonly used pyoderma gangrenosum diagnostic frameworks vary in sensitivity and that no single framework captured all expert-confirmed cases.
MULTIPLE SIMULTANEOUS SITES MAY SUGGEST A SYSTEMIC INFLAMMATORY PROCESS:
The simultaneous involvement of anatomically distinct sites (breast and back) suggests it would be less likely that local factors (infection, ischemia, implant complications) are the primary etiology. While bilateral breast pyoderma gangrenosum occurs as a complication in patients undergoing bilateral breast surgery, dual-site involvement at distant anatomic locations is rarely reported [1,2,5]. This multifocal pattern of postsurgical involvement may raise suspicion for an underlying systemic inflammatory process, though the extent to which this reflects a generalizable predisposition versus a case-specific confluence of pathergy and comorbid autoimmune disease (celiac) remains uncertain.
Although multifocal pyoderma gangrenosum is recognized in the general pyoderma gangrenosum literature, simultaneous involvement of multiple surgical sites in the postoperative setting has been commonly documented after bilateral breast procedures [6,9,10]. Involvement of both the primary surgical site and a distant donor site has also been reported [6]. The present case adds to this literature by demonstrating overlapping progression of postsurgical pyoderma gangrenosum at 2 anatomically distinct operative sites: the left superior breast and left lower back. In this case, the multifocal pattern contributed to suspicion for an inflammatory, pathergy-driven process, particularly given the lack of sustained response to antimicrobial therapy and repeated wound-directed interventions.
STEROID RESPONSE IS BOTH DIAGNOSTIC AND THERAPEUTIC:
Systemic corticosteroids remain first-line treatment for pyoderma gangrenosum, with a mean healing time of 4.5 months [1,11]. In this case, advanced biologic wound products were used before immunosuppression without sustained improvement and were later continued as adjunctive wound care after corticosteroid therapy was initiated. Because healing occurred only after the addition of topical and intralesional corticosteroids, the clinical course supports immunosuppression as the pivotal therapeutic shift. However, the relative contribution of adjunctive wound products cannot be determined from this single case.
LIMITATIONS:
This case has several limitations. As a single-case report, it cannot establish causality or determine whether the multifocal presentation reflects a generalizable PSPG pattern or a case-specific combination of pathergy, autoimmune history, and delayed wound healing. Diagnostic certainty was also limited by the absence of a clearly documented neutrophilic infiltrate on histopathology and by concurrent infectious findings, including pulmonary granulomatous inflammation with yeast forms and intermittent positive wound cultures.
Conclusions
This case highlights the diagnostic challenge of postsurgical pyoderma gangrenosum in patients with complex wound histories and competing explanations for poor healing. The unusual multifocal involvement of 2 anatomically distinct surgical sites, the left superior breast and left lower back, was a notable clinical feature that raised suspicion for an inflammatory, pathergy-driven process. Progressive breast and back ulceration despite debridement, antimicrobial therapy including both antibiotic and antifungal therapy, and advanced wound therapies underscored the need to reconsider PSPG when postsurgical wounds worsen despite appropriate treatment. This case also emphasizes that diagnostic criteria should be applied alongside clinical judgment, particularly when histopathologic findings are nonspecific, but the clinical pattern remains concerning for pyoderma gangrenosum. Earlier consideration of pyoderma gangrenosum in refractory postsurgical wounds may help avoid repeated procedural trauma, unnecessary treatment escalation, and prolonged morbidity.
Figures
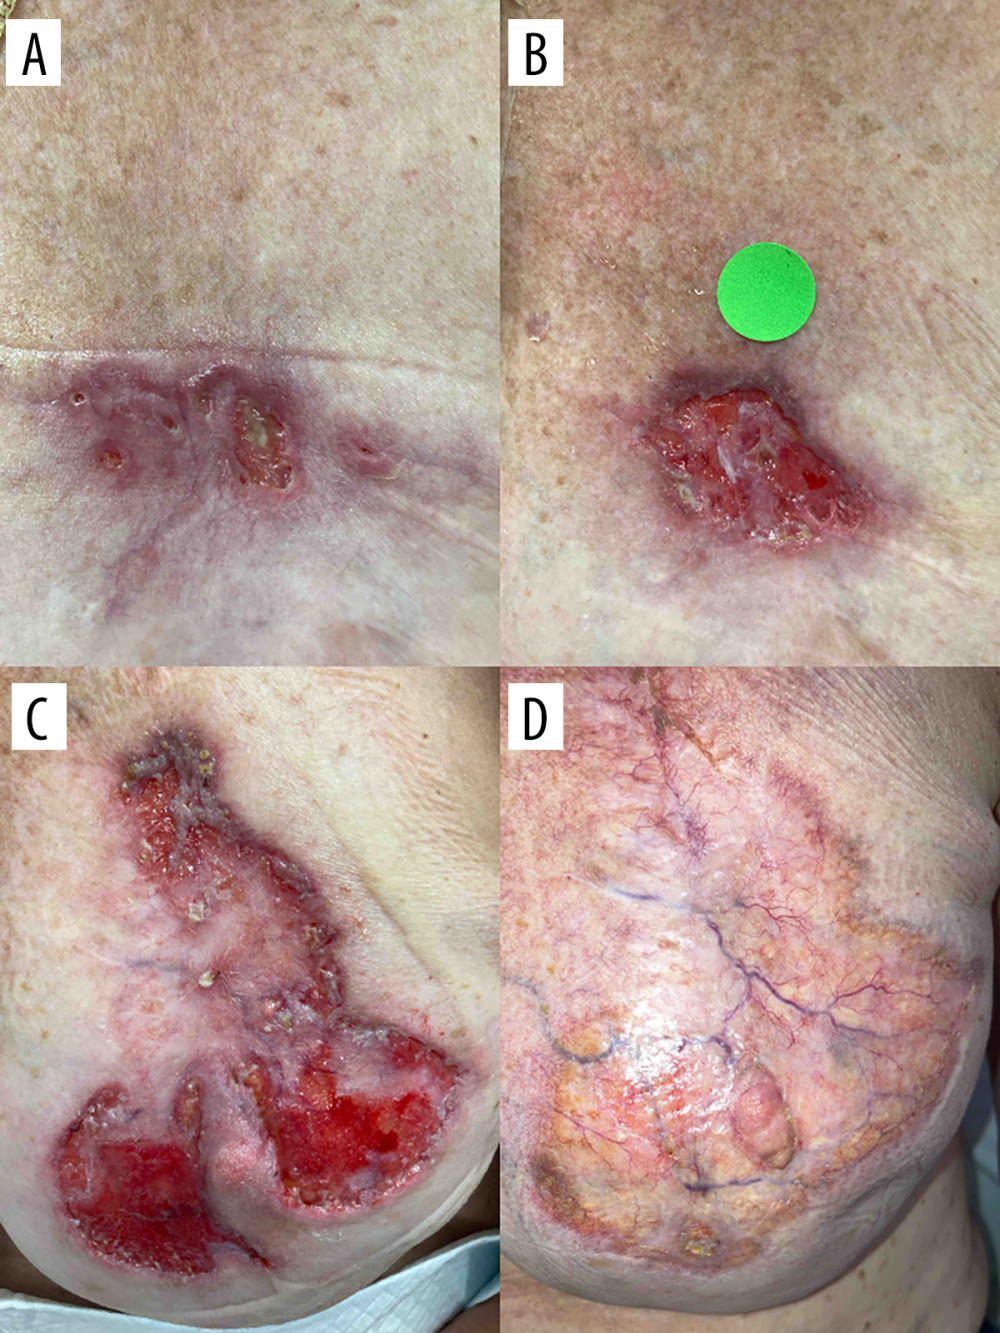 Figure 1. Clinical progression of the left breast lesion. (A) Initial presentation of the nonhealing left superior breast ulcer, measuring approximately 1.0 × 3.0 cm at the time of initial wound clinic evaluation. (B) Interval enlargement following serial debridement, with the lesion increasing to approximately 4.5 × 3.5 cm. (C) Peak lesion size prior to initiation of immunosuppressive therapy, measuring approximately 10.0 × 10.5 cm. (D) Complete resolution after initiation of immunosuppressive therapy. Images were obtained during routine clinical care; therefore, acquisition distance, angle, lighting, and scale were not fully standardized.
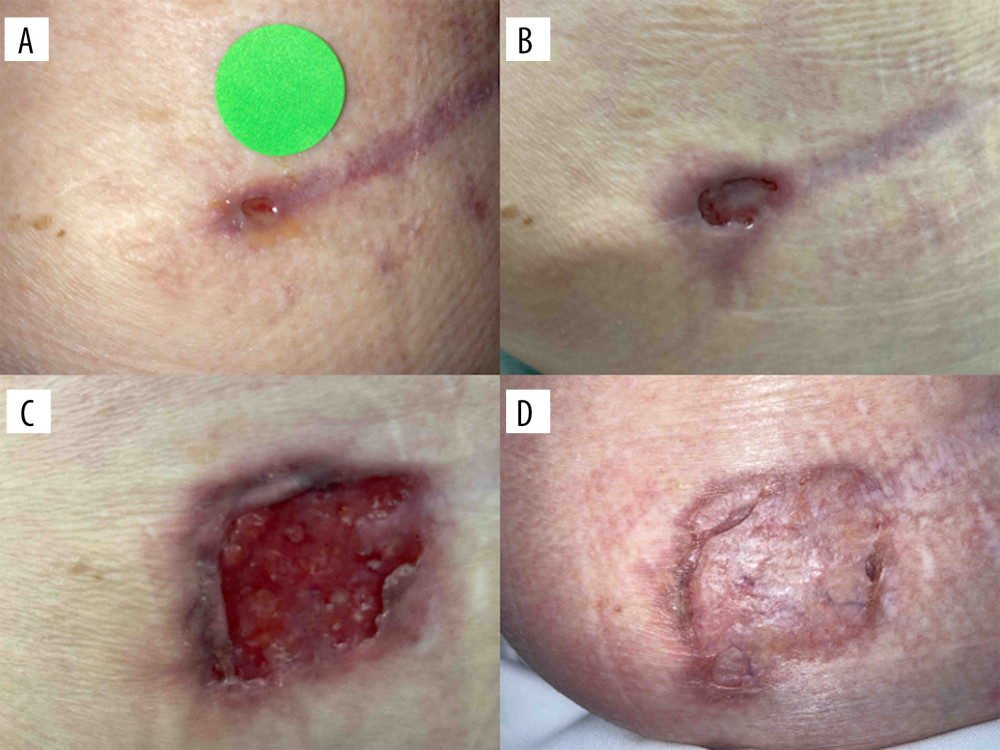 Figure 2. Clinical progression of the left lower back lesion. (A) Reopening of the left lower back wound, initially measuring approximately 0.2 × 0.5 cm. (B) Interval enlargement of the lower back lesion to approximately 0.9 × 1.2 cm. (C) Maximum lesion size prior to initiation of immunosuppressive therapy, measuring approximately 2.0 × 2.5 cm. (D) Complete resolution following immunosuppressive therapy. Images were obtained during routine clinical care; therefore, acquisition distance, angle, lighting, and scale were not fully standardized.
References
1. Caddia G, Voulliaume D, Dettori L, Postsurgical pyoderma gangrenosum in breast surgery: An updated systematic review, takeaways, and the 6 commandments: Aesthet Surg J, 2025; 45(9); NP142-NP53
2. Tolkachjov SN, Fahy AS, Cerci FB, Postoperative pyoderma gangrenosum: A clinical review of published cases: Mayo Clin Proc, 2016; 91(9); 1267-79
3. Zuo KJ, Fung E, Tredget EE, Lin AN, A systematic review of post-surgical pyoderma gangrenosum: Identification of risk factors and proposed management strategy: J Plast Reconstr Aesthet Surg, 2015; 68(3); 295-303
4. Bar D, Beberashvili I, Assessing the role of wound debridement in pyoderma gangrenosum – A retrospective cohort study: Wound Repair Regen, 2024; 32(6); 941-48
5. Tolkachjov SN, Fahy AS, Wetter DA, Postoperative pyoderma gangrenosum (PG): The Mayo Clinic experience of 20 years from 1994 through 2014: J Am Acad Dermatol, 2015; 73(4); 615-22
6. Tuffaha SH, Sarhane KA, Mundinger GS, Pyoderma gangrenosum after breast surgery: Diagnostic pearls and treatment recommendations based on a systematic literature review: Ann Plast Surg, 2016; 77(2); e39-44
7. Maverakis E, Ma C, Shinkai K, Diagnostic criteria of ulcerative pyoderma gangrenosum: A Delphi consensus of international experts: JAMA Dermatol, 2018; 154(4); 461-66
8. Haag C, Hansen T, Hajar T, Comparison of three diagnostic frameworks for pyoderma gangrenosum: J Invest Dermatol, 2021; 141(1); 59-63
9. Caldarola G, Traini DO, Falco GM, Clinical, epidemiological, and therapeutic hallmarks of pyoderma gangrenosum: A case series of 35 patients: Int J Dermatol, 2024; 63(9); 1185-92
10. Ashchyan HJ, Butler DC, Nelson CA, The association of age with clinical presentation and comorbidities of pyoderma gangrenosum: JAMA Dermatol, 2018; 154(4); 409
11. Maverakis E, Marzano AV, Le ST, Pyoderma gangrenosum: Nat Rev Dis Primers, 2020; 6(1); 81
Figures
Figure 1. Clinical progression of the left breast lesion. (A) Initial presentation of the nonhealing left superior breast ulcer, measuring approximately 1.0 × 3.0 cm at the time of initial wound clinic evaluation. (B) Interval enlargement following serial debridement, with the lesion increasing to approximately 4.5 × 3.5 cm. (C) Peak lesion size prior to initiation of immunosuppressive therapy, measuring approximately 10.0 × 10.5 cm. (D) Complete resolution after initiation of immunosuppressive therapy. Images were obtained during routine clinical care; therefore, acquisition distance, angle, lighting, and scale were not fully standardized.Figure 2. Clinical progression of the left lower back lesion. (A) Reopening of the left lower back wound, initially measuring approximately 0.2 × 0.5 cm. (B) Interval enlargement of the lower back lesion to approximately 0.9 × 1.2 cm. (C) Maximum lesion size prior to initiation of immunosuppressive therapy, measuring approximately 2.0 × 2.5 cm. (D) Complete resolution following immunosuppressive therapy. Images were obtained during routine clinical care; therefore, acquisition distance, angle, lighting, and scale were not fully standardized. In Press
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954119
Case report
Am J Case Rep In Press; DOI: 10.12659/AJCR.953323
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953894
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953804