


27 September 2026: Articles 
Pulmonary Actinomycosis Diagnosed via BALF mNGS in a 53-Year-Old Nonsmoking Man With Pneumoconiosis and Penicillin-Induced Thrombocytopenia: A Case Report
Unusual clinical course, Challenging differential diagnosis, Unusual or unexpected effect of treatment, Adverse events of drug therapy, Educational Purpose (only if useful for a systematic review or synthesis), Rare coexistence of disease or pathology
Xin Feng BE 1, Lin-yu Wang CE 2, Ni-jiao Li DE 1, Ze-qiang Lin F 1, He-ming Huang F 1, Yi-ling Xie F 1, Jie Liang F 1, Lunkai Yao F 1, Xin-yi Zhuo F 1, Yan Li DF 2*, Ye Qiu AG 1
DOI: 10.12659/AJCR.953438
Am J Case Rep 2026; 27:e953438


Abstract
BACKGROUND: Pulmonary actinomycosis is an uncommon infection with nonspecific clinical and radiologic features that can be difficult to distinguish from lung malignancy, tuberculosis, and other chronic pulmonary diseases. This report describes a patient with pneumoconiosis in whom bronchoalveolar lavage fluid (BALF) metagenomic next-generation sequencing (mNGS) provided important microbiologic evidence to support the diagnosis of pulmonary actinomycosis after inconclusive conventional evaluation.
CASE REPORT: A 53-year-old nonsmoking presented with a 1-month history of cough and hemoptysis. Chest computed tomography showed bilateral upper-lung masses, multiple nodules, and lymphadenopathy; he initially underwent right upper lobectomy because malignancy was suspected. Histopathologic examination showed necrotizing granulomatous inflammation with carbon deposition, but no specific pathogen was identified. Empirical antituberculosis treatment was ineffective. After transfer to our hospital, bronchoscopy was performed. Routine BALF culture and staining results were negative, whereas mNGS detected Actinomyces israelii. Intravenous ampicillin/sulbactam led to clinical and radiologic improvement, but severe thrombocytopenia developed. Platelet counts decreased again after subsequent penicillin exposure, supporting probable penicillin-induced thrombocytopenia. After discontinuation of penicillin and joint evaluation by respiratory physicians and clinical pharmacists, omadacycline was administered, followed by oral doxycycline. The patient displayed clinical improvement, platelet counts normalized, and follow-up imaging showed lesion absorption.
CONCLUSIONS: This case illustrates the diagnostic difficulty of pulmonary actinomycosis in a patient with pneumoconiosis and suggests that BALF mNGS can be helpful when routine studies are unrevealing. It also indicates that omadacycline is a feasible alternative when penicillin-associated thrombocytopenia prevents continuation of first-line therapy.
Keywords: Pneumoconiosis, Thrombocytopenia, Actinomycosis
Introduction
Pulmonary actinomycosis is an uncommon chronic bacterial infection caused by
The diagnosis of pulmonary actinomycosis can be challenging. Conventional culture has limited sensitivity because
Penicillin-based therapy is the standard treatment for pulmonary actinomycosis [4]. However, severe drug-induced thrombocytopenia may require interruption of first-line therapy and selection of an alternative antimicrobial agent [5]. This report describes a patient with pneumoconiosis and a pulmonary actinomycosis diagnosis supported by BALF mNGS, whose treatment course was complicated by probable penicillin-induced thrombocytopenia. It highlights the diagnostic contribution of BALF mNGS in a clinically challenging case of pulmonary actinomycosis, along with the use of omadacycline after penicillin was discontinued because of severe thrombocytopenia.
Case Report
A 53-year-old nonsmoking man presented with a 1-month history of cough and hemoptysis. He had initially been treated at a local clinic for presumed pneumonia with cefuroxime and levofloxacin, but his symptoms did not improve. Further evaluation showed negative results for serum 1,3-β-D-glucan, galactomannan, cryptococcal antigen, T-cell testing for tuberculosis infection, autoantibodies, and human immunodeficiency virus screening. Initial sputum and blood culture findings also were negative. Chest CT showed masses and nodules in both upper lobes with mediastinal lymphadenopathy (Figure 1A). Pulmonary tuberculosis was initially considered, and scar carcinoma could not be excluded. Thus, the patient underwent right upper lobectomy with lymph node dissection.
Postoperative histopathologic examination of the surgical specimen showed necrotizing granulomatous inflammation with carbon dust deposition (Figure 2A, 2B). Periodic acid-Schiff (PAS), PAS with diastase (PAS-D), and acid-fast staining results all were negative. On the basis of the pathologic findings and occupational history, pneumoconiosis with possible pulmonary tuberculosis was considered; empirical antituberculosis therapy with isoniazid, rifampin, ethambutol, and pyrazinamide was initiated. However, the response was poor. Two weeks later, the patient was admitted to our hospital because of worsening cough and new-onset yellow sputum production.
According to the patient, he had no smoking history and had worked in spray painting for 10 years. He also reported a history of eating wild bamboo rats. He had no recent travel history and had not taken any other medications before visiting the hospital. On admission, laboratory testing showed a white blood cell count of 14.28 × 10⁹/L (reference range, 3.5–9.5 × 10⁹/L), neutrophil proportion of 88.5% (reference range, 40%–75%), C-reactive protein level of 47.18 mg/L (reference range, 0–10 mg/L), and erythrocyte sedimentation rate of 75.2 mm/h (reference range, 0–15 mm/h). The CD3+CD4+ T-cell count was 396/μL (reference range, 550–1400/μL). Repeat chest CT showed a postoperative right-sided pneumothorax with persistent pulmonary nodules and lymphadenopathy (Figure 1B). Because the clinical course was inconsistent with an effective response to antituberculosis therapy, the initial working diagnosis was reconsidered.
Bronchoscopy was performed. BALF smear and culture results were negative. On admission day 15, BALF mNGS detected
Subsequently, the patient was given intravenous ampicillin/sulbactam. After 1 week, his symptoms improved, the C-reactive protein level returned to normal. However, the platelet count abruptly fell to 11 × 109/L (reference range, 125–350 × 109/L). He was urgently treated with platelet transfusion and recombinant human interleukin-11, and the platelet count gradually stabilized. On admission day 30, antimicrobial therapy was changed to intravenous penicillin sodium. After this change, the platelet count fell further to 1 × 10⁹/L, and petechiae developed on the extremities. Nevertheless, follow-up CT showed a reduction in pulmonary nodule size (Figure 1C).
A multidisciplinary clinical review was then undertaken. Sepsis, disseminated intravascular coagulation, autoimmune disease, and hematologic malignancy were excluded. The adverse drug reaction was assessed using the Naranjo scale, with a score of 8 (Table 1), supporting a diagnosis of penicillin-associated thrombocytopenia. Because penicillin could no longer be used, an alternative regimen was required. Considering the relatively low hematologic toxicity of tetracycline-class agents, omadacycline was initiated. After the change in treatment, the patient’s symptoms improved, and the platelet count remained stable. After 2 weeks of omadacycline, follow-up chest CT showed further radiologic improvement of the pulmonary lesions (Figure 1D). Treatment was then stepped down to oral doxycycline, and the patient was discharged.
At the 6-month follow-up, chest CT showed continued improvement of the pulmonary lesions (Figure 1E). The platelet count remained within the normal range (Figure 2C), and no recurrent life-threatening thrombocytopenia occurred. On January 10, 2025, BALF was sampled again for mNGS, which continued to detect
Discussion
Pulmonary actinomycosis remains a difficult clinical diagnosis because its symptoms, imaging findings, and even histopathologic features are often nonspecific [3]. Patients may present with cough, sputum production, hemoptysis, fever, mass-like lesions, nodules, cavitation, or lymphadenopathy; these findings can overlap with those of tuberculosis, lung cancer, or other chronic pulmonary infections [4]. Reported data indicate that the initial diagnostic accuracy is less than 4% to 7%; more than 25% of cases are misdiagnosed as lung cancer, and many others are misdiagnosed as tuberculosis [4,6,7]. In the present case, bilateral upper-lung masses and nodules with lymphadenopathy, along with necrotizing granulomatous inflammation on histopathology, initially raised concern regarding pulmonary tuberculosis and possible scar carcinoma. The diagnosis was further complicated by the patient’s pneumoconiosis, which contributed underlying structural lung disease and carbon dust deposition to the histopathologic background.
A central lesson from the present case is that pulmonary actinomycosis can remain unrecognized when routine microbiologic and histopathologic findings are nondiagnostic. In our patient, sputum culture, blood culture, BALF smear, BALF culture, and multiple serologic test results were negative. Histopathology showed necrotizing granulomatous inflammation, but special stains did not identify a specific pathogen. Although
The diagnosis of pneumoconiosis also warrants attention [9]. Our patient had a 10-year occupational history of spray-painting work, postoperative histopathology showed carbon dust deposition, and the imaging findings were consistent with chronic structural lung disease. These factors supported the diagnosis of pneumoconiosis and likely contributed to the diagnostic complexity [9]. Chronic lung injury and impaired local clearance may create a setting in which uncommon infections are more difficult to distinguish from malignancy, mycobacterial disease, or postoperative changes [1]. In our patient, pneumoconiosis was both a comorbidity and a contributing factor to diagnostic uncertainty early in the clinical course.
Another important feature of the present case was the treatment-limiting adverse drug reaction. Penicillin-based therapy remains the standard treatment for actinomycosis; our patient initially showed clinical, laboratory, and radiologic improvement after ampicillin/sulbactam. However, the abrupt decline in platelet count after β-lactam exposure, followed by a more severe recurrence upon administration of penicillin sodium, strongly suggested a drug-related cause. Other potential causes of thrombocytopenia (eg, sepsis, disseminated intravascular coagulation, autoimmune disease, and hematologic malignancy) were excluded during multidisciplinary evaluation. The Naranjo score was 8, supporting a probable drug-induced reaction [5]. In this context, continued penicillin therapy was inappropriate, and an alternative antimicrobial regimen was required.
Tetracyclines are recognized alternatives for the treatment of actinomycosis. In the present case, omadacycline, an aminomethylcycline, was selected after penicillin discontinuation because ongoing antimicrobial therapy was still required and additional hematologic toxicity was a major concern. Its selection was supported by several practical considerations [10–12]: preserved tetracycline activity despite common resistance mechanisms involving efflux pumps and ribosomal protection, in vitro activity against anaerobic gram-positive organisms, the absence of a clear association with thrombocytopenia in available clinical data, and the convenience of both intravenous and oral administration without routine renal or hepatic dose adjustment.
After omadacycline had been initiated, the patient’s respiratory symptoms improved, platelet counts remained stable, and follow-up imaging showed continued radiologic improvement. He was subsequently transitioned to oral doxycycline and remained clinically stable during follow-up. Although no broad treatment recommendation can be made based on a single case, the present clinical course suggests that omadacycline is a reasonable alternative for selected patients with pulmonary actinomycosis when penicillin cannot be continued because of severe thrombocytopenia.
The present case also highlights the value of multidisciplinary management in complex infectious diseases. Final diagnosis and treatment decisions were not based on a single test result or the opinion of a single specialty. Instead, the case required integration of respiratory assessment, histopathology, microbiologic testing, adverse drug reaction evaluation, and antimicrobial decision-making. Collaboration between treating physicians and clinical pharmacists was particularly important after the onset of severe thrombocytopenia, when balancing antimicrobial efficacy and drug safety became the central management challenge. In this setting, multidisciplinary review strengthened the diagnostic reasoning and facilitated safer transition of antimicrobial therapy.
Some limitations should be acknowledged. First, this is a single case report, and its findings cannot be generalized. Second, the diagnosis of pulmonary actinomycosis was supported by BALF mNGS rather than by culture isolation or demonstration of sulfur granules; notably, the result was consistent with the overall clinical context and treatment response. Third, detailed antimicrobial susceptibility data were unavailable. Finally, although the temporal association and Naranjo score supported penicillin-associated thrombocytopenia, drug-specific immunologic testing was not performed.
In summary, the present case demonstrates that pulmonary actinomycosis in a patient with pneumoconiosis can present a serious diagnostic challenge when routine studies are inconclusive and more common conditions are initially favored. It also suggests that BALF mNGS may provide useful adjunctive diagnostic evidence in such settings and that omadacycline may be considered when penicillin therapy must be discontinued because of severe thrombocytopenia.
Conclusions
Pulmonary actinomycosis should be considered in patients with chronic pulmonary lesions when routine microbiologic study findings are negative and the clinical course is inconsistent with the initial diagnosis. In the present case, BALF mNGS provided useful adjunctive diagnostic evidence. When penicillin therapy could not be continued because of severe thrombocytopenia, omadacycline was successfully used as salvage therapy.
Figures
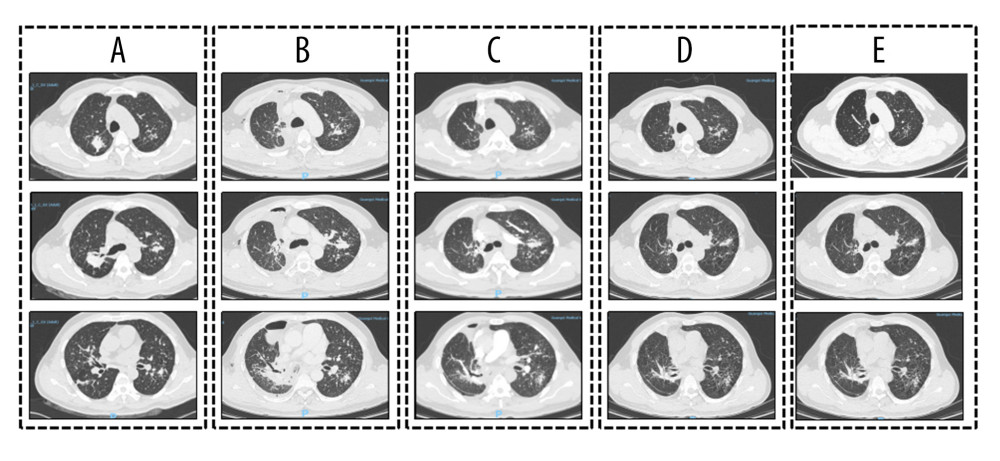 Figure 1. Chest computed tomography (CT) findings at various clinical stages(A) Before surgery: CT images show irregular contrast-enhanced soft-tissue masses in the bilateral upper lungs, multiple bilateral solid nodules, and enlarged lymph nodes in the right supraclavicular fossa and mediastinum. (B) After surgery and 2 weeks of antituberculosis therapy (isoniazid, rifampin, ethambutol, and pyrazinamide): CT images show postoperative distortion of the right lung architecture, right hydropneumothorax, persistent bilateral solid nodules without appreciable interval resolution, and persistent lymphadenopathy in the right supraclavicular fossa and mediastinum. (C) After 12 days of treatment with penicillin sodium: CT images show prominent resolution of the pulmonary lesions compared with previous images. (D) After 2 weeks of omadacycline treatment: CT images show further interval resolution of the pulmonary lesions. (E) After 4 weeks of omadacycline followed by 6 months of doxycycline treatment: CT images show continued resolution and improvement of the pulmonary lesions.
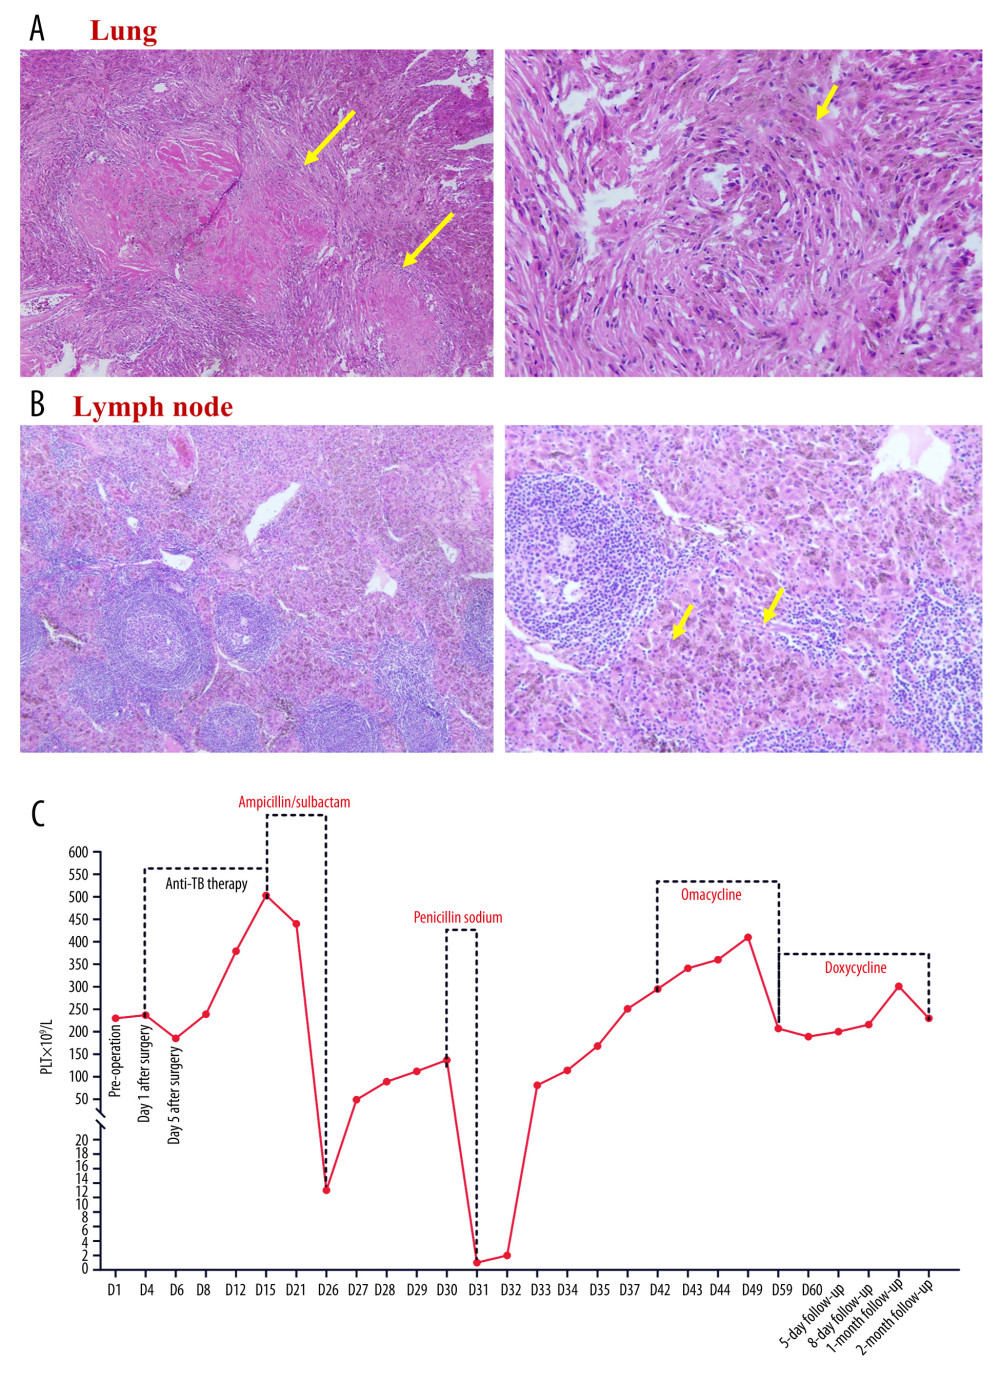 Figure 2. Histopathologic and hematologic findings(A, B) Histopathologic examination of the surgical lung and lymph node specimens showed necrotizing granulomatous inflammation with carbon deposition and numerous macrophages containing carbon particles. (C) Changes in platelet count during the treatment course. Abbreviations: PLT, platelets; TB, tuberculosis.
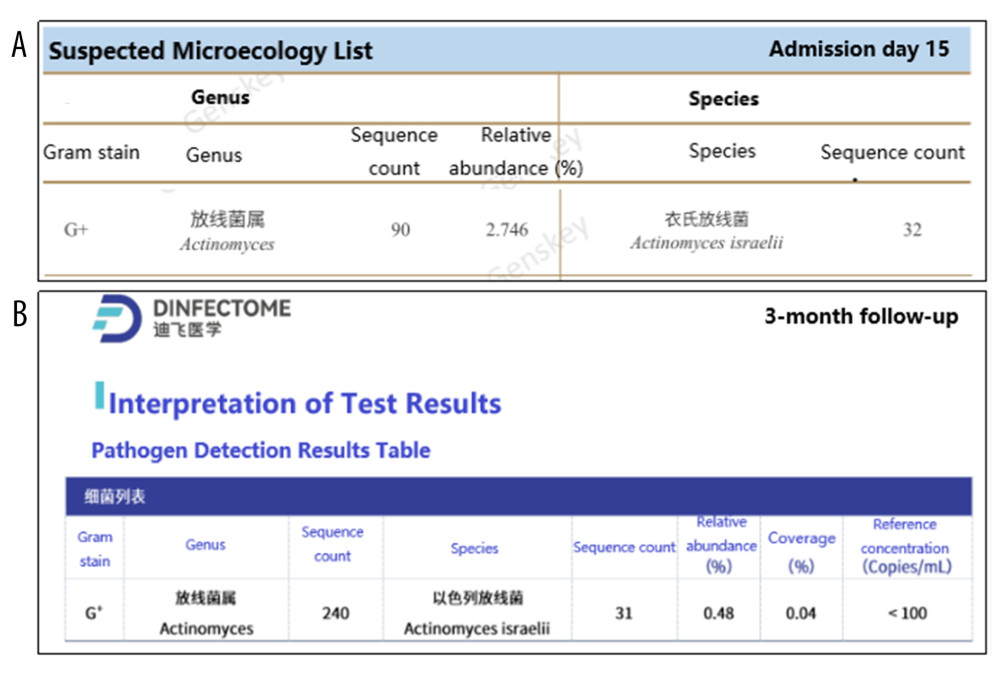 Figure 3. Serial BALF mNGS resultsImage shows BALF mNGS findings from admission day 15 (A), and 3-month follow-up (B). In panel A, Actinomyces israelii was identified as a suspected pathogenic microorganism, with 32 sequence reads. In panel B, Actinomyces israelii was identified as a pathogenic microorganism, with 31 sequence reads. Abbreviations: BALF, bronchoalveolar lavage fluid; mNGS, metagenomic next-generation sequencing.
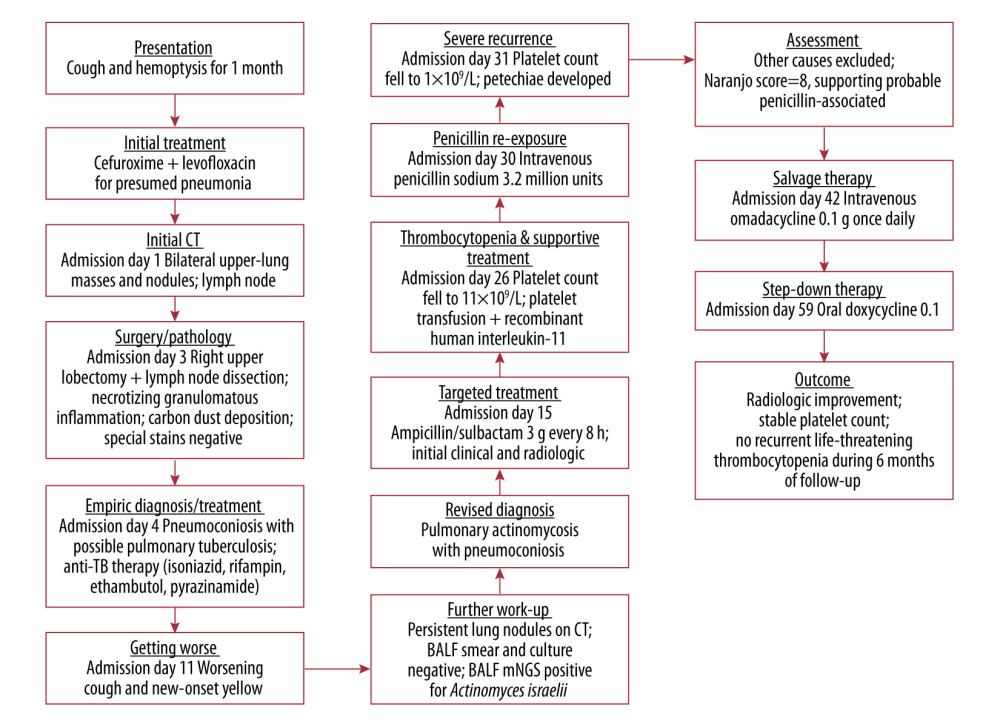 Figure 4. Clinical timeline of diagnosis and treatmentAbbreviations: BALF, bronchoalveolar lavage fluid; CT, computed tomography; TB, tuberculosis.
Tables
Table 1. Naranjo scale.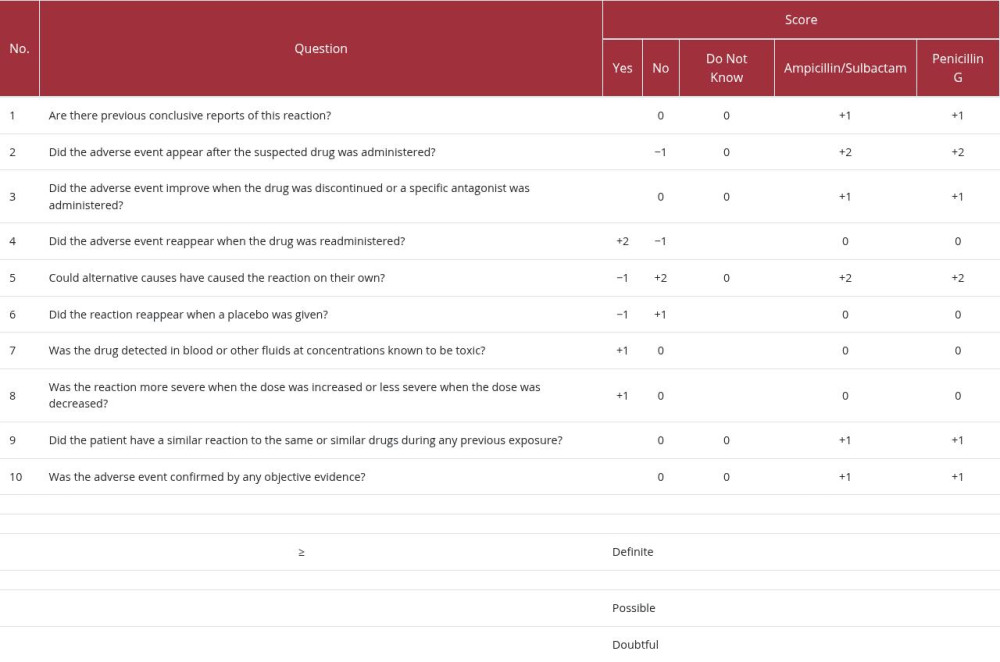
References
1. GBD 2019 Chronic Respiratory Diseases Collaborators, Global burden of chronic respiratory diseases and risk factors, 1990–2019. An update from the Global Burden of Disease Study 2019: EClinicalMedicine, 2023; 59; 101936
2. Yuan X, Xie L, Shi Z, Zhou M, Application of mNGS in the study of pulmonary microbiome in pneumoconiosis complicated with pulmonary infection patients and exploration of potential biomarkers: Front Cell Infect Microbiol, 2023; 13; 1200157
3. Kho SS, Ganapaty S, Omar N, Opportunistic actinomycosis in pulmonary alveolar proteinosis: Thorax, 2022; 77(8); 842-43
4. Boot M, Archer J, Ali I, The diagnosis and management of pulmonary actinomycosis: J Infect Public Health, 2023; 16(4); 490-500
5. Qayum I, Naeem A, Khan UI, Anwar S, Abdullah HM, Tazobactam-piperacillin associated transient neutropenia and thrombocytopenia: Am J Ther, 2022; 29(6); e712-14
6. Suzuki M, Araki K, Matsubayashi S, A case of recurrent hemoptysis caused by pulmonary actinomycosis diagnosed using transbronchial lung biopsy after bronchial artery embolism and a brief review of the literature: Ann Transl Med, 2019; 7(5); 108
7. Mabeza GF, Macfarlane J, Pulmonary actinomycosis: Eur Respir J, 2003; 21(3); 545-51
8. Wang W, Ren D, Xu C, Pulmonary actinomycosis diagnosed by radial endobronchial ultrasound coupled with metagenomic next-generation sequencing: A case report and brief literature review: Int J Infect Dis, 2020; 100; 379-81
9. Peng Y, Li X, Cai S, Prevalence and characteristics of COPD among pneumoconiosis patients at an occupational disease prevention institute: A cross-sectional study: BMC Pulm Med, 2018; 18(1); 22
10. Tanaka SK, Steenbergen J, Villano S, Discovery, pharmacology, and clinical profile of omadacycline, a novel aminomethylcycline antibiotic: Bioorg Med Chem, 2016; 24(24); 6409-19
11. Noel GJ, Draper MP, Hait H, A randomized, evaluator-blind, phase 2 study comparing the safety and efficacy of omadacycline to those of linezolid for treatment of complicated skin and skin structure infections: Antimicrob Agents Chemother, 2012; 56(11); 5650-54
12. Marini I, Uzun G, Jamal K, Bakchoul T, Treatment of drug-induced immune thrombocytopenias: Haematologica, 2022; 107(6); 1264-77
Figures
Figure 1. Chest computed tomography (CT) findings at various clinical stages(A) Before surgery: CT images show irregular contrast-enhanced soft-tissue masses in the bilateral upper lungs, multiple bilateral solid nodules, and enlarged lymph nodes in the right supraclavicular fossa and mediastinum. (B) After surgery and 2 weeks of antituberculosis therapy (isoniazid, rifampin, ethambutol, and pyrazinamide): CT images show postoperative distortion of the right lung architecture, right hydropneumothorax, persistent bilateral solid nodules without appreciable interval resolution, and persistent lymphadenopathy in the right supraclavicular fossa and mediastinum. (C) After 12 days of treatment with penicillin sodium: CT images show prominent resolution of the pulmonary lesions compared with previous images. (D) After 2 weeks of omadacycline treatment: CT images show further interval resolution of the pulmonary lesions. (E) After 4 weeks of omadacycline followed by 6 months of doxycycline treatment: CT images show continued resolution and improvement of the pulmonary lesions.Figure 2. Histopathologic and hematologic findings(A, B) Histopathologic examination of the surgical lung and lymph node specimens showed necrotizing granulomatous inflammation with carbon deposition and numerous macrophages containing carbon particles. (C) Changes in platelet count during the treatment course. Abbreviations: PLT, platelets; TB, tuberculosis.Figure 3. Serial BALF mNGS resultsImage shows BALF mNGS findings from admission day 15 (A), and 3-month follow-up (B). In panel A, Actinomyces israelii was identified as a suspected pathogenic microorganism, with 32 sequence reads. In panel B, Actinomyces israelii was identified as a pathogenic microorganism, with 31 sequence reads. Abbreviations: BALF, bronchoalveolar lavage fluid; mNGS, metagenomic next-generation sequencing.Figure 4. Clinical timeline of diagnosis and treatmentAbbreviations: BALF, bronchoalveolar lavage fluid; CT, computed tomography; TB, tuberculosis. In Press
Case report
Am J Case Rep In Press; DOI: 10.12659/AJCR.953469
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954338
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.953196
Case report 
Am J Case Rep In Press; DOI: 10.12659/AJCR.954118
Most Viewed Current Articles
07 Dec 2021 : Case report  27,648,584
DOI :10.12659/AJCR.934347
Am J Case Rep 2021; 22:e934347
06 Dec 2021 : Case report  180,102
DOI :10.12659/AJCR.934406
Am J Case Rep 2021; 22:e934406
21 Jun 2024 : Case report
123,811
DOI :10.12659/AJCR.944371
Am J Case Rep 2024; 25:e944371
08 May 2026 : Case report
93,777
DOI :10.12659/AJCR.952158
Am J Case Rep 2026; 27:e952158